Indications
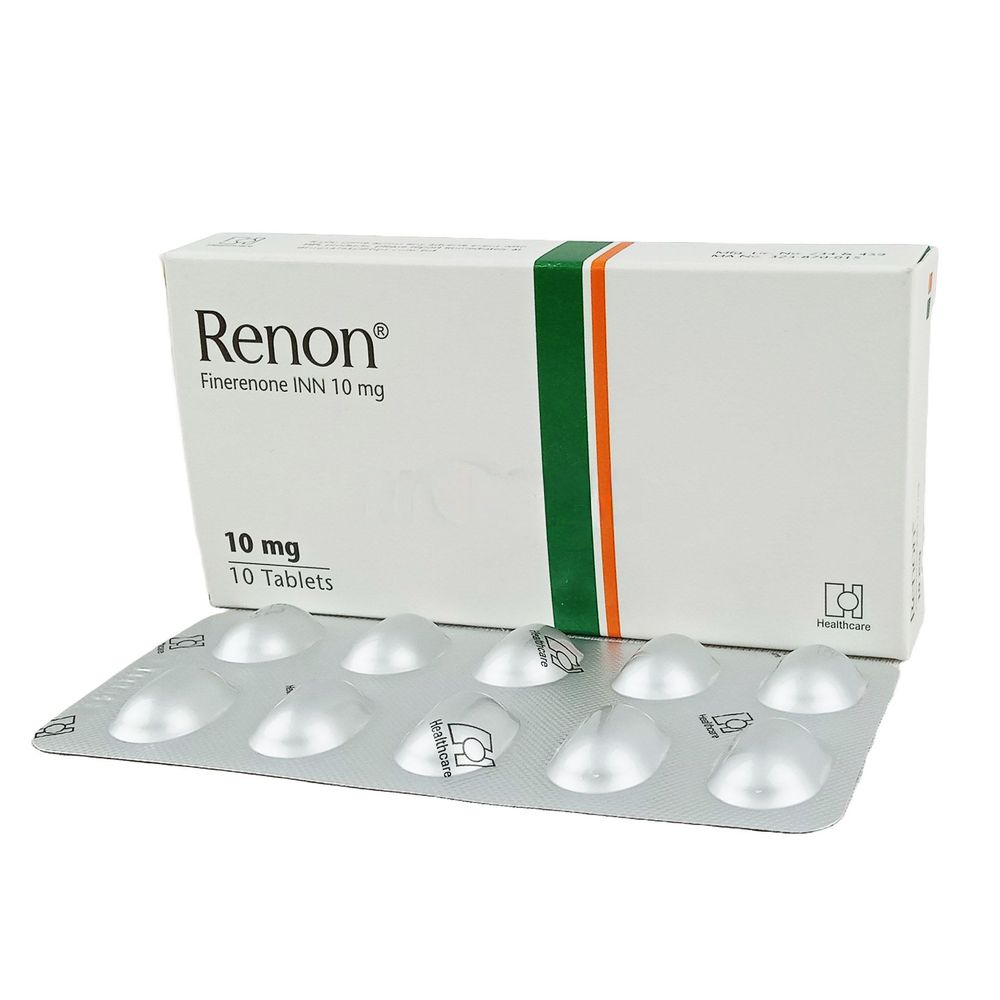
Renon Tablet (Finerenone) is indicated to reduce the risk of:
- Sustained decline in estimated glomerular filtration rate (eGFR)
- End-stage kidney disease (ESKD)
- Cardiovascular death
- Non-fatal myocardial infarction (heart attack)
- Hospitalization due to heart failure
in adult patients with chronic kidney disease (CKD) associated with Type 2 Diabetes (T2D).
Pharmacology
Finerenone is a non-steroidal, selective mineralocorticoid receptor (MR) antagonist. The MR is activated by aldosterone and cortisol and regulates gene transcription. Finerenone blocks MR-mediated sodium reabsorption and prevents MR overactivation in both epithelial tissues (such as the kidneys) and non-epithelial tissues (such as the heart and blood vessels).
MR overactivation is believed to contribute to fibrosis and inflammation. Finerenone has high potency and selectivity for MR and has no significant affinity for androgen, progesterone, estrogen, or glucocorticoid receptors.
In patients treated with Finerenone:
- Mean systolic blood pressure decreased by approximately 3 mmHg
- Mean diastolic blood pressure decreased by approximately 1–2 mmHg during the first month and remained stable thereafter
Even at four times the maximum approved dose, Finerenone does not cause clinically significant QT interval prolongation.
Pharmacokinetics
Absorption
- Completely absorbed after oral administration
- Absolute bioavailability: 44%
- Peak plasma concentration (Cmax) reached within 0.5 to 1.25 hours after dosing
- Food has no clinically significant effect on absorption
Distribution
- Volume of distribution (Vss): 52.6 L
- Plasma protein binding: approximately 92%, mainly to serum albumin
Elimination
- Terminal half-life: approximately 2–3 hours
- Systemic blood clearance: approximately 25 L/hour
Metabolism
- Primarily metabolized by CYP3A4 (90%)
- Secondarily metabolized by CYP2C8 (10%)
- Metabolites are inactive
Excretion
- Approximately 80% of the administered dose is excreted through urine
Dosage and Administration
Recommended Starting Dose
- eGFR ≥60 mL/min/1.73 m²: 20 mg once daily
- eGFR ≥25 to <60 mL/min/1.73 m²: 10 mg once daily
- eGFR <25 mL/min/1.73 m²: Not recommended
After 4 weeks, the dose may be increased to 20 mg once daily depending on eGFR and serum potassium levels.
- Can be taken with or without food.
- Tablets may be crushed and mixed with water or soft food for patients who cannot swallow whole tablets.
Monitoring and Dose Adjustment
- Target dose: 20 mg once daily
- Measure serum potassium 4 weeks after starting treatment
- Continue monitoring potassium after dose adjustments and throughout therapy
- Adjust dose as necessary according to potassium levels
Missed Dose
If a dose is missed:
- Take it as soon as remembered on the same day
- If not possible, skip the missed dose and continue with the next scheduled dose
- Do not take a double dose
Drug Interactions
Strong CYP3A4 Inhibitors
- Contraindicated with Renon
- Increase Finerenone exposure and risk of adverse effects
- Avoid grapefruit and grapefruit juice
Moderate and Weak CYP3A4 Inhibitors
- May increase Finerenone exposure
- Monitor serum potassium levels
- Dose adjustment may be required
Strong and Moderate CYP3A4 Inducers
- May decrease Finerenone exposure
- Can reduce effectiveness
- Avoid concomitant use
Contraindications
Renon is contraindicated in:
- Patients receiving strong CYP3A4 inhibitors
- Patients with adrenal insufficiency
Side Effects
Common adverse reactions (≥1% and more frequent than placebo):
- Hyperkalemia (high potassium levels)
- Hypotension (low blood pressure)
- Hyponatremia (low sodium levels)
Pregnancy and Lactation
There are no adequate data regarding the use of Finerenone during pregnancy.
Animal studies have shown developmental toxicity at exposures approximately four times higher than those expected in humans, although the clinical significance is not clear.
The background risk of major birth defects, miscarriage, or adverse pregnancy outcomes in the indicated population is unknown.
All pregnancies carry some inherent risk of birth defects, pregnancy loss, or other adverse outcomes.