Search products by name
Search medicines by name
0
0 item
৳ 0.00
Your Complete HealthCare Solution - Right Here


10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.
৳ 0.00
10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.


Products

Payment

Delivery
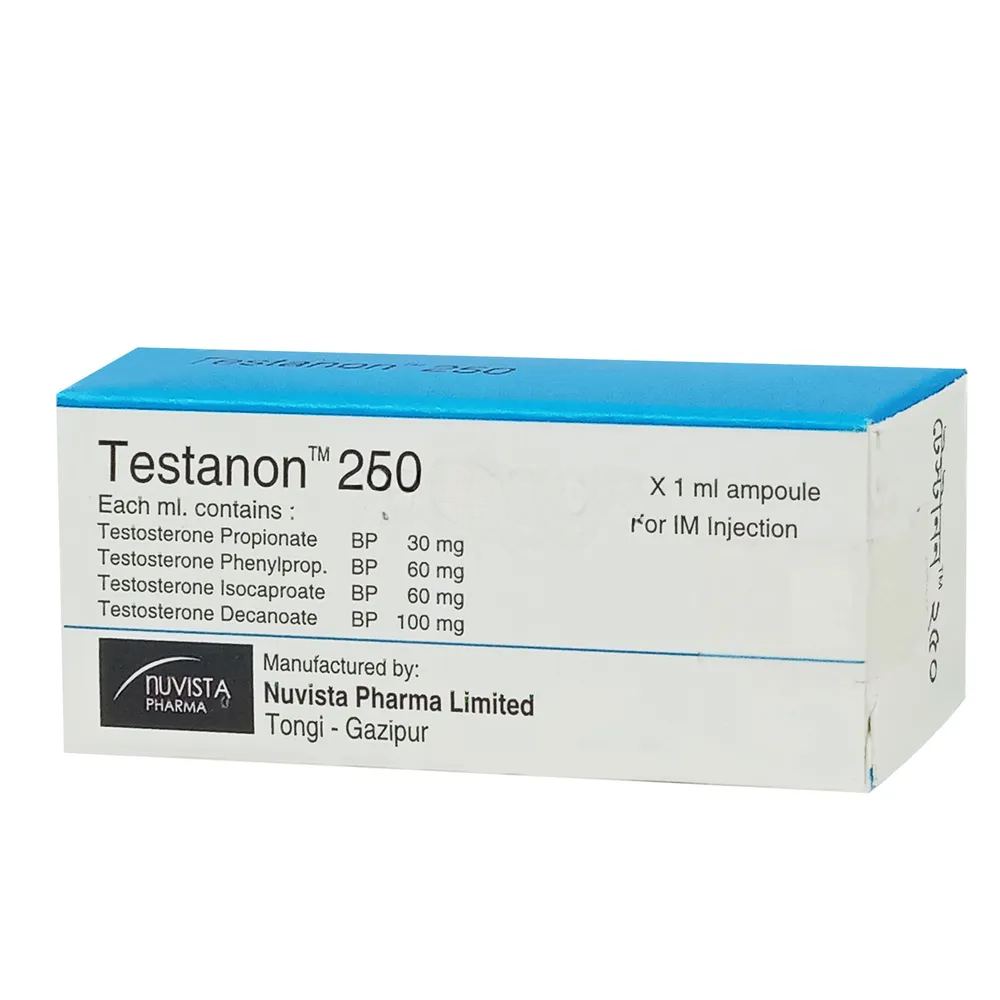
Testosterone replacement therapy
Intramuscular\r\nMale hypogonadism\r\nAdult: By deep IM injection 1 ml usually 1 to 4 weeks. \r\nDosage is based on your medical condition, testosterone blood levels, and response to treatment.
Hypercalcaemia or hypercalciuria, males with breast or prostate carcinoma. Pregnancy and lactation.
Testosterone is the principal endogenous androgen responsible for promoting the growth and development of male sexual organs and maintaining secondary sex characteristics in androgen-deficient males.
Cardiovascular disorders, skeletal metastases, renal or hepatic impairment, epilepsy, migraine, diabetes or other conditions which may be aggravated by fluid retention, eg heart failure. Elderly, prepubertal boys. Monitor signs of virilization (females) and development of priapism or excessive sexual stimulation (males). Periodic haemoglobin, lipid determinations and rectal prostate examination.
Fluid and electrolyte retention; increased vascularity of the skin; hypercalcaemia, impaired glucose tolerance; increased bone growth and skeletal weight; increase LDL cholesterol; increase haematocrit and fibrinolytic activity; headache, depression and GI bleeding. \r\nMales: spermatogenesis suppression, priapism, gynaecomastia, prostatic hyperplasia and accelerate growth of malignant prostate neoplasms. \r\nFemales: suppression of lactation, ovarian activity and menstruation; virilization, clitoris hypertrophy, increased libido, oily skin, acne, hirsutism, male pattern baldness. \r\n\r\nIM: urticaria, inflammation at Inj site, postinjection induration, furunculosis.\r\n\r\nPotentially Fatal: Peliosis hepatis, liver toxicity, malignant neoplasm.\r\n
Enhance activities of ciclosporine, antidiabetics, thyroxine, anticoagulants. Long term use of testosterone may cause resistance to effects of neuromuscular blockers. Enhance fluid retention from corticosteroids.
Testosterone replacement therapy
Intramuscular\r\nMale hypogonadism\r\nAdult: By deep IM injection 1 ml usually 1 to 4 weeks. \r\nDosage is based on your medical condition, testosterone blood levels, and response to treatment.
Hypercalcaemia or hypercalciuria, males with breast or prostate carcinoma. Pregnancy and lactation.
Testosterone is the principal endogenous androgen responsible for promoting the growth and development of male sexual organs and maintaining secondary sex characteristics in androgen-deficient males.
Cardiovascular disorders, skeletal metastases, renal or hepatic impairment, epilepsy, migraine, diabetes or other conditions which may be aggravated by fluid retention, eg heart failure. Elderly, prepubertal boys. Monitor signs of virilization (females) and development of priapism or excessive sexual stimulation (males). Periodic haemoglobin, lipid determinations and rectal prostate examination.
Fluid and electrolyte retention; increased vascularity of the skin; hypercalcaemia, impaired glucose tolerance; increased bone growth and skeletal weight; increase LDL cholesterol; increase haematocrit and fibrinolytic activity; headache, depression and GI bleeding. \r\nMales: spermatogenesis suppression, priapism, gynaecomastia, prostatic hyperplasia and accelerate growth of malignant prostate neoplasms. \r\nFemales: suppression of lactation, ovarian activity and menstruation; virilization, clitoris hypertrophy, increased libido, oily skin, acne, hirsutism, male pattern baldness. \r\n\r\nIM: urticaria, inflammation at Inj site, postinjection induration, furunculosis.\r\n\r\nPotentially Fatal: Peliosis hepatis, liver toxicity, malignant neoplasm.\r\n
Enhance activities of ciclosporine, antidiabetics, thyroxine, anticoagulants. Long term use of testosterone may cause resistance to effects of neuromuscular blockers. Enhance fluid retention from corticosteroids.
Use in Hypogonadism