Search products by name
Search medicines by name
0
0 item
৳ 0.00
Your Complete HealthCare Solution - Right Here


10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.
৳ 0.00
10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.


Quantity:

Products

Payment

Delivery
Peptic ulcer disease, H. pylori infection, Gastro-oesophageal reflux disease, Zollinger-Ellison syndrome, Oesophagitis, Acid-related dyspepsia, NSAID-associated ulceration, ulcer resistant to H2 receptor antagonists, Gastrointestinal (GI) bleeding from stress, Prophylaxis for acid aspiration syndrome during induction of anaesthesia
Controlled-release: Should be taken on an empty stomach. Take 1 hr before meals. Swallow whole, do not chew/crush.\r\nNormal release: May be taken with or without food.\r\n\r\nIV Preparation\r\nGERD with a history of erosive esophagitis\r\n15-min infusion: Reconstitute with 10 mL NS, THEN further dilute with 100 mL D5W, NS, or LR to final concentration of 0.4 mg/mL\r\n\r\nZollinger-Ellison syndrome\r\n15-min infusion: Reconstitute each vial with 10 mL NS, THEN\r\nCombine 2 vials and further dilute with 80 mL D5W, NS, or LR to total volume of 100 mL (concentration 0.8 mg/mL)\r\n2-min injection: Reconstitute with 10 mL NS to final concentration of 4 mg/mL\r\n\r\nIV Administration\r\nInfuse over 15 min no more than 3 mg/min (7 mL/min) for GERD and 6 mg/min (7 mL/min) for pathologic hypersecretory conditions
Erosive Esophagitis Associated With GERD\r\nTreatment: 40 mg PO qDay for 8-16 weeks\r\nMaintenance of healing: 40 mg PO qDay\r\nAlternatively, 40 mg IV qDay for 7-10 days\r\n\r\nShort-term Treatment of GERD\r\nOral therapy inappropriate or not possible: 40 mg IV infusion over 15 minutes qDay for 7-10 days; switch to PO once patient able to swallow\r\n\r\nZollinger-Ellison Syndrome\r\n40 mg PO qDay; up to 240 mg/day administered in some patients\r\n80 mg IV infusion q8-12hr up to 7 days; switch to PO once patient able to swallow\r\n\r\nPeptic Ulcer Disease \r\nDuodenal ulcer: 40 mg PO qDay for 2-4 weeks\r\nGastric ulcer: 40 mg PO qDay for 4-8 weeks\r\n\r\nElderly: No dosage adjustment needed.\r\n\r\nHepatic impairment: Max: 20 mg/day or 40 mg on alternate days.
Erosive Esophagitis Associated With GERD\r\n<5 years: Safety and efficacy not established\r\n>5 years\r\n15 kg to <40 kg: 20 mg PO qDay for up to 8 weeks\r\n40 kg or greater: 40 mg PO qDay for up to 8 weeks
Renal impairment: No dosage adjustment needed.\r\n
Concomitant use w/ rilpivirine, atazanavir and nelfinavir. Lactation.
Pantoprazole is a substituted benzimidazole, and also known as PPI due to its property to block the final step of acid secretion by inhibiting H+/K+ ATPase enzyme system in gastric parietal cell. Both basal and stimulated acid are inhibited.
Gastric malignancy should be ruled out. Consider Zn++ supplementation during IV therapy in patients who are prone to Zn++ deficiency. Pregnancy. Monitoring Parameters Monitor Mg levels prior to initiation and periodically during prolonged use.\r\n\r\nLactation\r\nRisk Summary\r\nPantoprazole has been detected in breast milk of a nursing mother after a single 40 mg oral dose of pantoprazole. There were no effects on the breastfed infant. There are no data on pantoprazole effects on milk production.\r\nThe developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for PROTONIX and any potential adverse effects on the breastfed child from pantoprazole or from the underlying maternal condition.
1-10%\r\nHeadache (>4%),Abdominal pain (4%),Facial edema (<4%),Generalized edema (<2%),Chest pain (4%),Diarrhea (4%),Constipation (<4%),Pruritus (4%),Rash (4%),Flatulence (<4%),Hyperglycemia (1%),Nausea (1%),Vomiting (>4%),Photosensitivity (<2%)\r\n\r\nFrequency Not Defined\r\nAngioedema,Atrophic gastritis,Anterior ischemic optic neuropathy,Hepatocellular damage leading to hepatic failure,Interstitial nephritis,Pancreatitis,Pancytopenia,Rhabdomyolysis,Risk of anaphylaxis,Stevens-Johnson syndrome,Fatal toxic epidermal necrolysis,Erythema multiforme
Risk Summary\r\nAvailable data from published observational studies did not demonstrate an association of major malformations or other adverse pregnancy outcomes with pantoprazole.\r\nIn animal reproduction studies, no evidence of adverse development outcomes was observed with pantoprazole. Reproduction studies have been performed in rats at oral doses up to 450 mg/kg/day (about 88 times the recommended human dose) and rabbits at oral doses up to 40 mg/kg/day (about 16 times the recommended human dose) with administration of pantoprazole during organogenesis in pregnant animals and have revealed no evidence of harm to the fetus due to pantoprazole in this study.
Increased risk of digoxin-induced cardiotoxic effects. Increased risk of hypomagnesaemia w/ diuretics. May increase INR and prothrombin time of warfarin. May increase serum concentration of methotrexate and saquinavir. Delayed absorption and decreased bioavailability w/ sucralfate. Decreased absorption of ketoconazole, itraconazole.\r\n\r\nPotentially Fatal: May decrease serum levels and pharmacological effects of rilpivirine, atazanavir and nelfinavir.
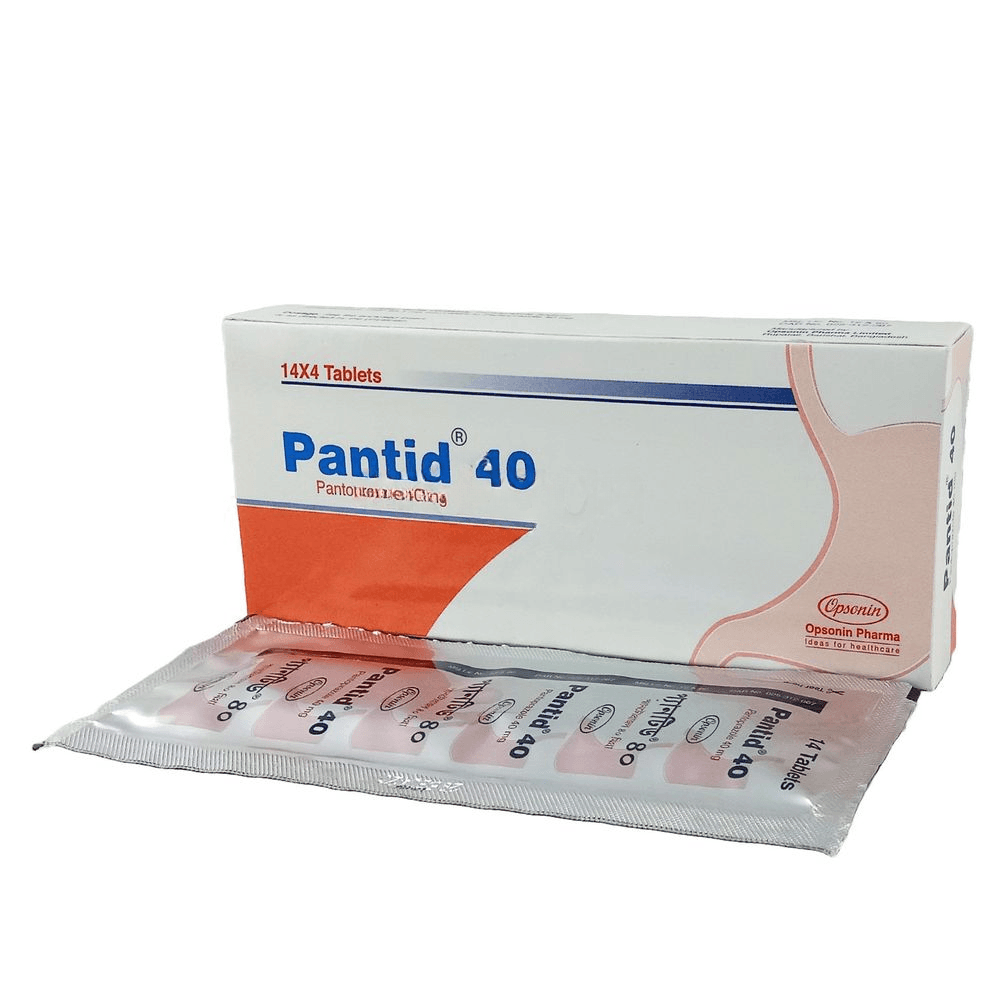
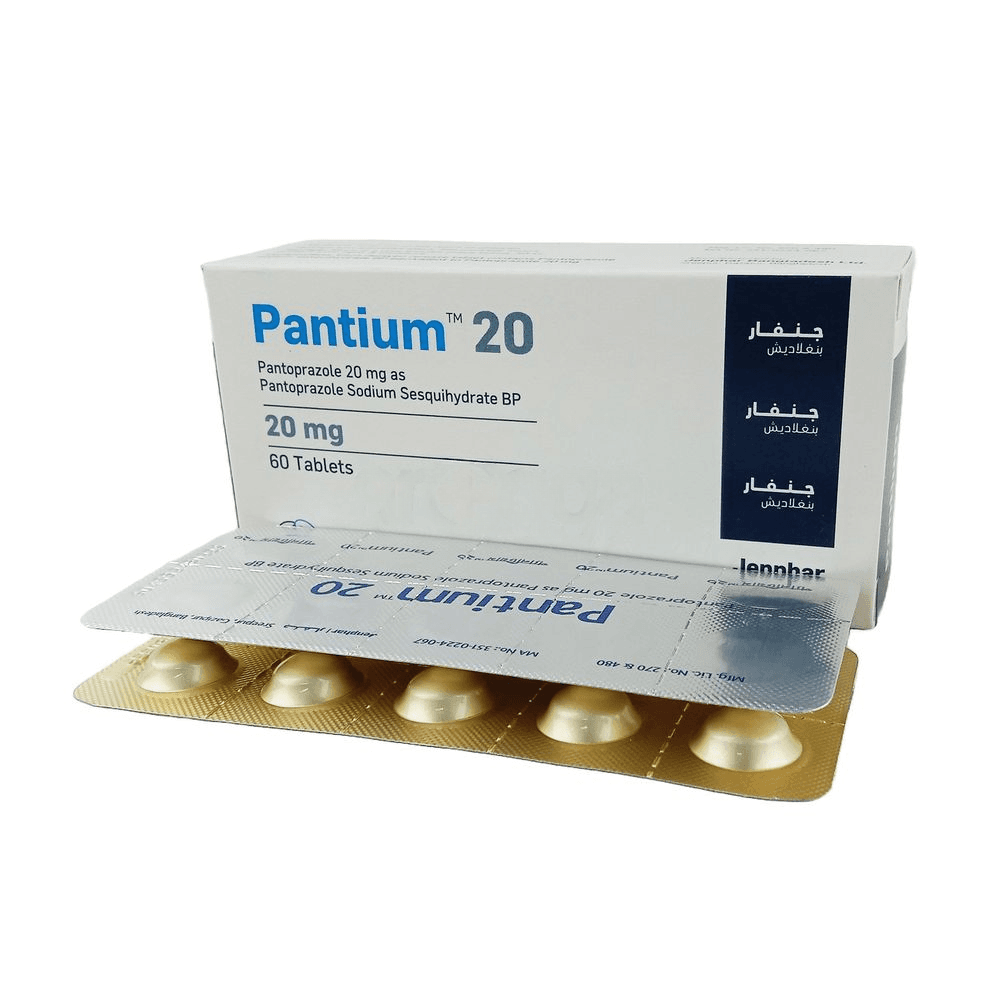

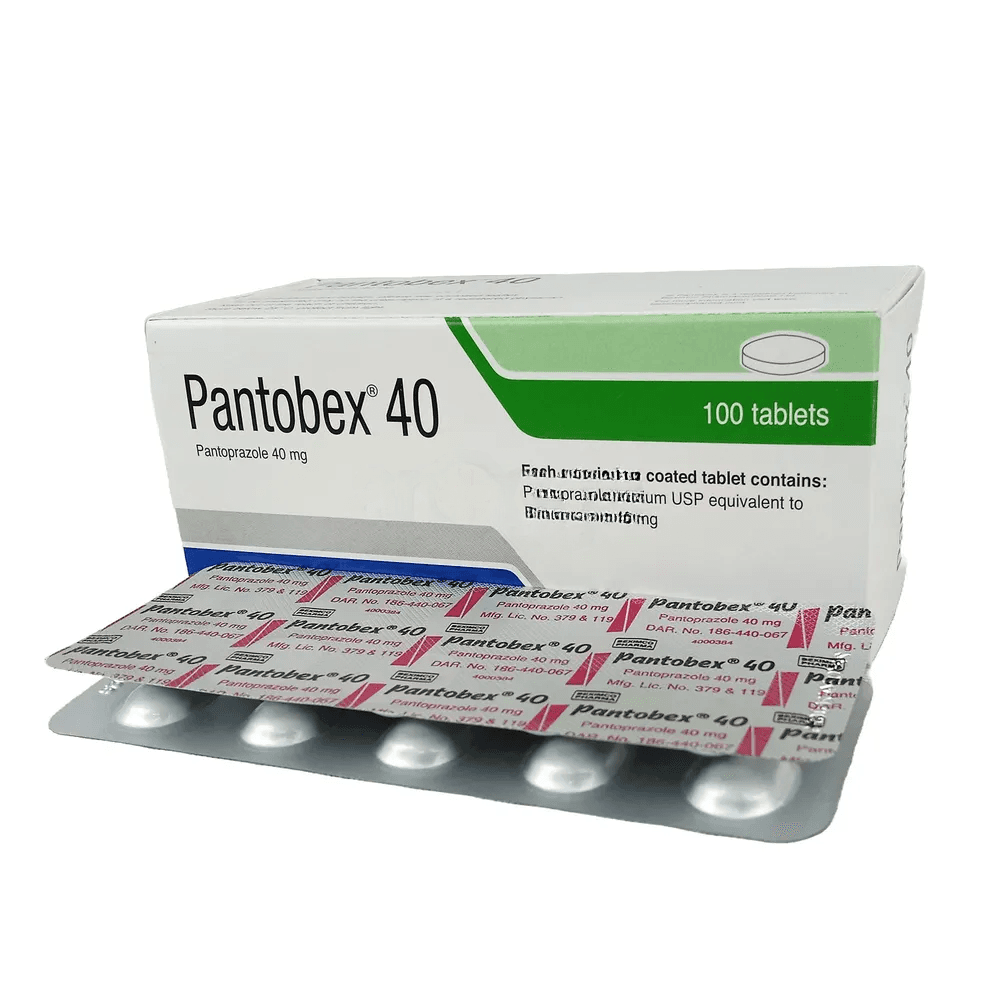
Peptic ulcer disease, H. pylori infection, Gastro-oesophageal reflux disease, Zollinger-Ellison syndrome, Oesophagitis, Acid-related dyspepsia, NSAID-associated ulceration, ulcer resistant to H2 receptor antagonists, Gastrointestinal (GI) bleeding from stress, Prophylaxis for acid aspiration syndrome during induction of anaesthesia
Controlled-release: Should be taken on an empty stomach. Take 1 hr before meals. Swallow whole, do not chew/crush.\r\nNormal release: May be taken with or without food.\r\n\r\nIV Preparation\r\nGERD with a history of erosive esophagitis\r\n15-min infusion: Reconstitute with 10 mL NS, THEN further dilute with 100 mL D5W, NS, or LR to final concentration of 0.4 mg/mL\r\n\r\nZollinger-Ellison syndrome\r\n15-min infusion: Reconstitute each vial with 10 mL NS, THEN\r\nCombine 2 vials and further dilute with 80 mL D5W, NS, or LR to total volume of 100 mL (concentration 0.8 mg/mL)\r\n2-min injection: Reconstitute with 10 mL NS to final concentration of 4 mg/mL\r\n\r\nIV Administration\r\nInfuse over 15 min no more than 3 mg/min (7 mL/min) for GERD and 6 mg/min (7 mL/min) for pathologic hypersecretory conditions
Erosive Esophagitis Associated With GERD\r\nTreatment: 40 mg PO qDay for 8-16 weeks\r\nMaintenance of healing: 40 mg PO qDay\r\nAlternatively, 40 mg IV qDay for 7-10 days\r\n\r\nShort-term Treatment of GERD\r\nOral therapy inappropriate or not possible: 40 mg IV infusion over 15 minutes qDay for 7-10 days; switch to PO once patient able to swallow\r\n\r\nZollinger-Ellison Syndrome\r\n40 mg PO qDay; up to 240 mg/day administered in some patients\r\n80 mg IV infusion q8-12hr up to 7 days; switch to PO once patient able to swallow\r\n\r\nPeptic Ulcer Disease \r\nDuodenal ulcer: 40 mg PO qDay for 2-4 weeks\r\nGastric ulcer: 40 mg PO qDay for 4-8 weeks\r\n\r\nElderly: No dosage adjustment needed.\r\n\r\nHepatic impairment: Max: 20 mg/day or 40 mg on alternate days.
Erosive Esophagitis Associated With GERD\r\n<5 years: Safety and efficacy not established\r\n>5 years\r\n15 kg to <40 kg: 20 mg PO qDay for up to 8 weeks\r\n40 kg or greater: 40 mg PO qDay for up to 8 weeks
Renal impairment: No dosage adjustment needed.\r\n
Concomitant use w/ rilpivirine, atazanavir and nelfinavir. Lactation.
Pantoprazole is a substituted benzimidazole, and also known as PPI due to its property to block the final step of acid secretion by inhibiting H+/K+ ATPase enzyme system in gastric parietal cell. Both basal and stimulated acid are inhibited.
Gastric malignancy should be ruled out. Consider Zn++ supplementation during IV therapy in patients who are prone to Zn++ deficiency. Pregnancy. Monitoring Parameters Monitor Mg levels prior to initiation and periodically during prolonged use.\r\n\r\nLactation\r\nRisk Summary\r\nPantoprazole has been detected in breast milk of a nursing mother after a single 40 mg oral dose of pantoprazole. There were no effects on the breastfed infant. There are no data on pantoprazole effects on milk production.\r\nThe developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for PROTONIX and any potential adverse effects on the breastfed child from pantoprazole or from the underlying maternal condition.
1-10%\r\nHeadache (>4%),Abdominal pain (4%),Facial edema (<4%),Generalized edema (<2%),Chest pain (4%),Diarrhea (4%),Constipation (<4%),Pruritus (4%),Rash (4%),Flatulence (<4%),Hyperglycemia (1%),Nausea (1%),Vomiting (>4%),Photosensitivity (<2%)\r\n\r\nFrequency Not Defined\r\nAngioedema,Atrophic gastritis,Anterior ischemic optic neuropathy,Hepatocellular damage leading to hepatic failure,Interstitial nephritis,Pancreatitis,Pancytopenia,Rhabdomyolysis,Risk of anaphylaxis,Stevens-Johnson syndrome,Fatal toxic epidermal necrolysis,Erythema multiforme
Risk Summary\r\nAvailable data from published observational studies did not demonstrate an association of major malformations or other adverse pregnancy outcomes with pantoprazole.\r\nIn animal reproduction studies, no evidence of adverse development outcomes was observed with pantoprazole. Reproduction studies have been performed in rats at oral doses up to 450 mg/kg/day (about 88 times the recommended human dose) and rabbits at oral doses up to 40 mg/kg/day (about 16 times the recommended human dose) with administration of pantoprazole during organogenesis in pregnant animals and have revealed no evidence of harm to the fetus due to pantoprazole in this study.
Increased risk of digoxin-induced cardiotoxic effects. Increased risk of hypomagnesaemia w/ diuretics. May increase INR and prothrombin time of warfarin. May increase serum concentration of methotrexate and saquinavir. Delayed absorption and decreased bioavailability w/ sucralfate. Decreased absorption of ketoconazole, itraconazole.\r\n\r\nPotentially Fatal: May decrease serum levels and pharmacological effects of rilpivirine, atazanavir and nelfinavir.
N/A