Search products by name
Search medicines by name
0
0 item
৳ 0.00
Your Complete HealthCare Solution - Right Here


10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.
৳ 0.00
10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.



Quantity:

Products

Payment

Delivery
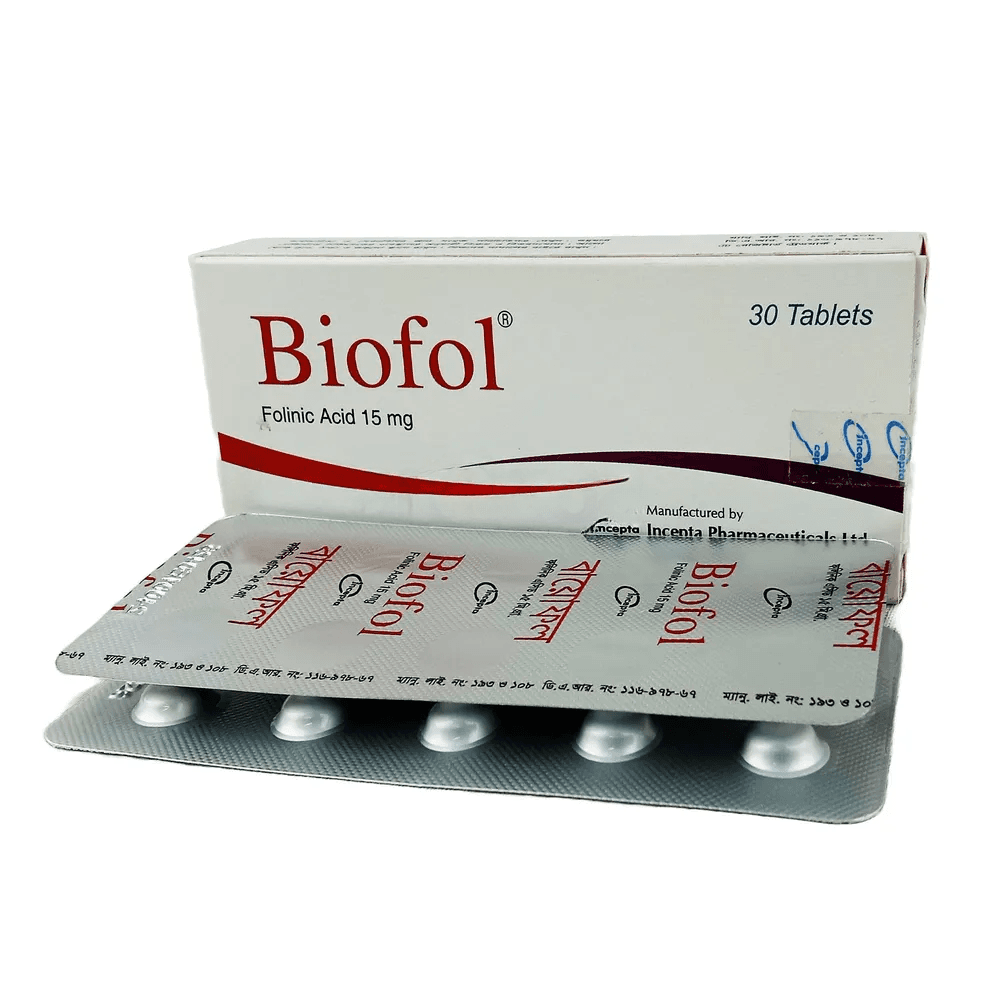
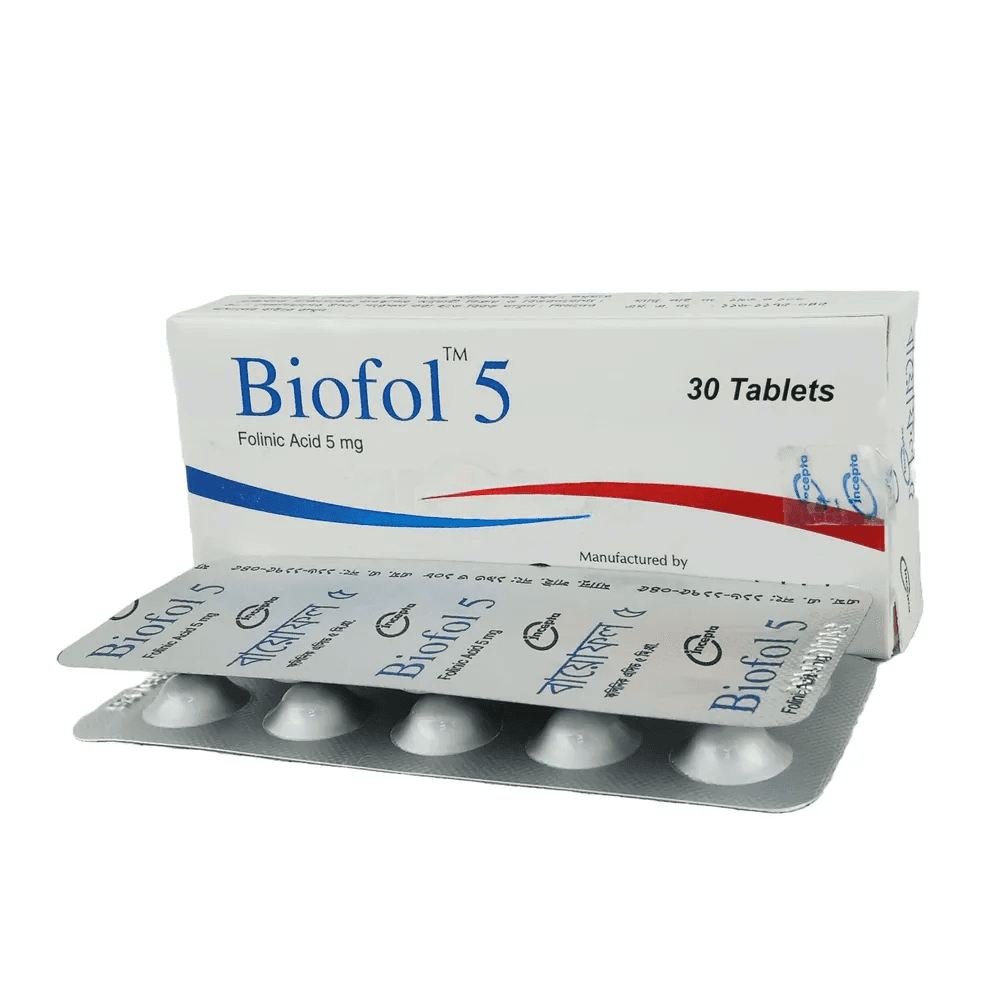
Indications: Folinic acid is indicated for neutralizing the immediate toxic effects of folic acid antagonists such as methotrexate. Calcium folinate rescue is a treatment technique used in conjunction with folic acid antagonists to minimize systemic toxicity. It is also used in the treatment of megaloblastic anemias due to nutritional deficiency, pregnancy, infancy, liver disease, and malabsorption syndromes.
Composition: Each tablet contains:
Calcium Folinate Hydrate 6.249 mg equivalent to Folinic Acid 5 mg
Calcium Folinate Hydrate 10.746 mg equivalent to Folinic Acid 15 mg
Pharmacology: Calcium folinate is the calcium salt of folinic acid, the active metabolite of folic acid. It acts as a cofactor in one-carbon transfer reactions during the biosynthesis of purines and pyrimidines in nucleic acids. Deficiency of folic acid impairs thymidylate synthesis, leading to defective DNA synthesis and megaloblastic anemia. Folinic acid rapidly converts to tetrahydrofolate derivatives and serves as a potent antidote to the hematopoietic and gastrointestinal toxicity of folic acid antagonists such as methotrexate, pyrimethamine, and trimethoprim.
Dosage & Administration:
Folinic Acid Rescue: Should begin as soon as possible after inadvertent methotrexate overdose and within 24 hours of administration. Typical regimen: 15 mg (approx. 10 mg/m²) every 6 hours for 10 doses.
Megaloblastic anemia: 5–15 mg daily.
Children and adolescents: Safety and efficacy not established.
Neutralizing toxicity: Folinic acid dose may equal or exceed the methotrexate dose if overdose is suspected.
Interactions: High doses may counteract the antiepileptic effects of phenobarbital, phenytoin, and primidone, increasing seizure risk. Concurrent use with fluoropyrimidines has been associated with seizures and syncope.
Contraindications:
Known hypersensitivity to calcium folinate or any component
Pernicious anemia or other megaloblastic anemia due to vitamin B12 deficiency
Rare hereditary problems of galactose intolerance, lactase deficiency, or glucose-galactose malabsorption
Side Effects: Most common: mucositis, stomatitis, leukopenia, and/or diarrhea (dose-limiting).
Pregnancy & Lactation: No adequate studies in pregnant women. Should only be used if potential benefit outweighs risk. Unknown if excreted in human milk; caution advised in nursing mothers.
Precautions & Warnings:
Should only be used with methotrexate or 5-FU under supervision of an experienced clinician.
Must be administered promptly after folic acid antagonist overdose; delay beyond 4 hours may reduce effectiveness.
Should not be given simultaneously with folic acid antagonists to abort toxicity, as therapeutic effect may be nullified.
Adequate hydration and urine alkalinization are essential during methotrexate therapy.
Overdose Effects: No specific antidote. Excessive folinate may nullify the therapeutic effect of folic acid antagonists. Supportive care recommended.
Therapeutic Class: Supportive Care Therapy
Storage Conditions: Store below 30°C. Protect from light and keep out of reach of children.

Colorectal cancer, Methotrexate toxicity, Megaloblastic anaemia
Oral\r\nAntidote for methotrexate toxicity\r\nAdult: 15 mg every 6 hr for 10 doses starting 24 hr after the start of methotrexate infusion. Continue admin until serum levels of methotrexate is <0.05 micromolar. \r\nMay also be given via IM/IV inj. \r\n\r\nFolate-deficient megaloblastic anaemia\r\nAdult: 15 mg daily. \r\n\r\nIntravenous\r\nAdjunct to fluorouracil in colorectal cancer\r\nAdult: 200 mg/m2 BSA by slow IV inj over at least 3 min followed by 370 mg/m2 fluorouracil by IV inj. Treatment is given for 5 consecutive days and repeated at intervals of 28 days for 2 courses. Subsequently, may repeat at 4-5 wkly intervals if the patient has recovered completely from the toxic effects of the prior treatment course. \r\n\r\nIntramuscular\r\nFolate-deficient megaloblastic anaemia\r\nAdult: Up to 1 mg/day.
Hypersensitivity, pernicious anaemia and other megaloblastic anaemias secondary to vit B12-deficiency, intrathecal and intraventricular admin.
Calcium folinate enters the cells as 5-methyl tetrahydrofolate and supplies the cofactor blocked by methotrexate. It stabilises the binding of 5-dUMP and thrymidylate synthetase, enhances flourouracil activity and neutralises the effects of folic acid antagonists such as methotrexate but increases those of 5-fluorouracil.
Undiagnosed megaloblastic anaemia, folate dependent tumors; pregnancy. Monitor calcium levels in patients receiving combined 5-Fluorouracil/Folinic acid treatment. To be given parenterally in the presence of GI toxicity, nausea or vomiting. Monitor serum levels of methotrexate to determine the optimal dose and duration of folinic acid admin. Monitor CBC, electrolytes and liver function tests before and regularly during treatment.
Allergic sensitisation, rash, pruritus, eythema, urticaria, nausea, vomiting, pyrexia.
Fluorouracil: Folinic acid may increase the toxicity associated with fluorouracil if the two are administered together. Some adverse effects that have occurred, particularly in elderly patients, include severe enterocolitis, diarrhea, and dehydration.\r\n\r\nSulfamethoxazole-trimethoprim: A potential drug interaction exists with concomitant use of sulfamethoxazole-trimethoprim and folinic acid. Folinic acid has been shown to decrease the efficacy of sulfamethoxazole-trimethoprim in the treatment of pneumocystis carinii, a common cause of pneumonia in AIDs patients
N/A