Search products by name
Search medicines by name
0
0 item
৳ 0.00
Your Complete HealthCare Solution - Right Here


10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.
৳ 0.00
10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.

Products

Payment

Delivery
Type 2 Diabetes Mellitus
Take in the morning qDay, with or without food
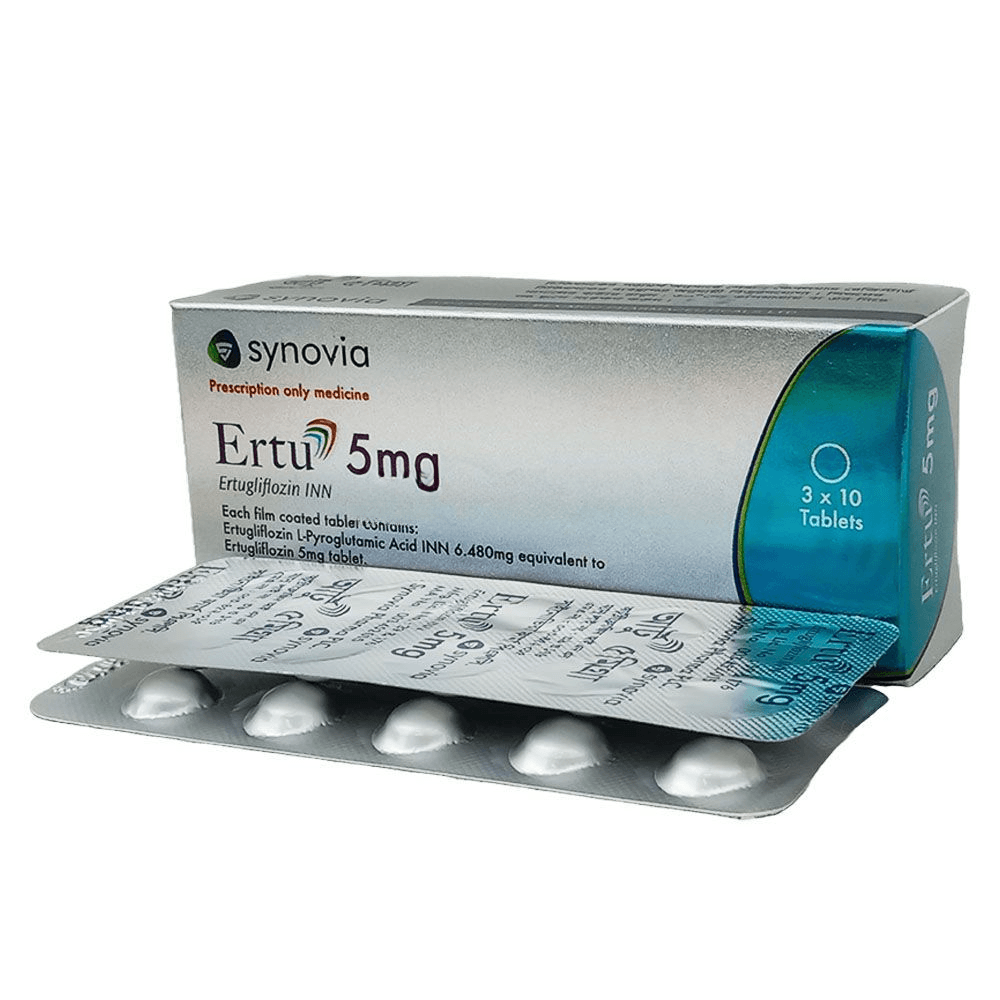
Type 2 Diabetes Mellitus\r\nIndicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus\r\n\r\nRecommended starting dose is 5 mg PO qDay in the morning\r\n\r\nIf starting dose tolerated and additional glycemic control is needed, increase dose to maximum of 15 mg qDay\r\n\r\nHepatic impairment\r\nMild-to-moderate: No dosage adjustment necessary\r\nSevere: Not recommended
<18 years: Safety and efficacy not established
Renal impairment\r\neGFR ?60 mL/min/1.73 m²: No dosage adjustment necessary\r\neGFR <30 mL/min/1.73 m²: Contraindicated\r\nEnd-stage renal disease or dialysis: Contraindicated\r\neGFR 30-60 mL/min/1.73 m²\r\nInitiation of ertugliflozin not recommended\r\nContinued use not recommended with persistent eGFR 30-60 mL/min/1.73 m²
Hypersensitivity\r\n\r\nSevere renal impairment, end-stage renal disease, or dialysis
Selective sodium-glucose transporter-2 (SGLT2) inhibitor\r\n\r\nSGLT-2 inhibition lowers the renal glucose threshold (ie, the plasma glucose concentration, which exceeds the maximum glucose reabsorption capacity of the kidney); lowering the renal glucose threshold results in increased urinary glucose excretion
$4e
>10%\r\nFemale genital mycotic infections (9.1-12.2%)\r\n\r\n1-10%\r\nVolume depletion adverse effects (1.9-4.4%)\r\n\r\nMale genital mycotic infections (3.7-4.2%)\r\n\r\nUrinary tract infections (4-4.1%)\r\n\r\nHeadache (2.9-3.5%)\r\n\r\nVaginal pruritus (2.4-2.8%)\r\n\r\nIncreased urination (2.4-2.7%)\r\n\r\nNasopharyngitis (2-2.5%)\r\n\r\nBack pain (1.7-2.5%)\r\n\r\nRenal adverse effects (1.3-2.5%)\r\n\r\nWeight decreased (1.2-2.4%)\r\n\r\nThirst (1.4-2.7%)
$4f
Hypoglycemia risk increased with insulin and insulin secretagogues (eg, sulfonylureas); a lower dose of insulin or insulin secretagogue may be required\r\nMonitoring glycemic control with urine glucose tests is not recommended in patients taking SGLT2 inhibitors, as SGLT2 inhibitors, increase urinary glucose excretion and lead to positive urine glucose tests; use alternative methods to monitor glycemic control
Type 2 Diabetes Mellitus
Take in the morning qDay, with or without food
Type 2 Diabetes Mellitus\r\nIndicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus\r\n\r\nRecommended starting dose is 5 mg PO qDay in the morning\r\n\r\nIf starting dose tolerated and additional glycemic control is needed, increase dose to maximum of 15 mg qDay\r\n\r\nHepatic impairment\r\nMild-to-moderate: No dosage adjustment necessary\r\nSevere: Not recommended
<18 years: Safety and efficacy not established
Renal impairment\r\neGFR ?60 mL/min/1.73 m²: No dosage adjustment necessary\r\neGFR <30 mL/min/1.73 m²: Contraindicated\r\nEnd-stage renal disease or dialysis: Contraindicated\r\neGFR 30-60 mL/min/1.73 m²\r\nInitiation of ertugliflozin not recommended\r\nContinued use not recommended with persistent eGFR 30-60 mL/min/1.73 m²
Hypersensitivity\r\n\r\nSevere renal impairment, end-stage renal disease, or dialysis
Selective sodium-glucose transporter-2 (SGLT2) inhibitor\r\n\r\nSGLT-2 inhibition lowers the renal glucose threshold (ie, the plasma glucose concentration, which exceeds the maximum glucose reabsorption capacity of the kidney); lowering the renal glucose threshold results in increased urinary glucose excretion
$4e
>10%\r\nFemale genital mycotic infections (9.1-12.2%)\r\n\r\n1-10%\r\nVolume depletion adverse effects (1.9-4.4%)\r\n\r\nMale genital mycotic infections (3.7-4.2%)\r\n\r\nUrinary tract infections (4-4.1%)\r\n\r\nHeadache (2.9-3.5%)\r\n\r\nVaginal pruritus (2.4-2.8%)\r\n\r\nIncreased urination (2.4-2.7%)\r\n\r\nNasopharyngitis (2-2.5%)\r\n\r\nBack pain (1.7-2.5%)\r\n\r\nRenal adverse effects (1.3-2.5%)\r\n\r\nWeight decreased (1.2-2.4%)\r\n\r\nThirst (1.4-2.7%)
$4f
Hypoglycemia risk increased with insulin and insulin secretagogues (eg, sulfonylureas); a lower dose of insulin or insulin secretagogue may be required\r\nMonitoring glycemic control with urine glucose tests is not recommended in patients taking SGLT2 inhibitors, as SGLT2 inhibitors, increase urinary glucose excretion and lead to positive urine glucose tests; use alternative methods to monitor glycemic control
N/A