Search products by name
Search medicines by name
0
0 item
৳ 0.00
Your Complete HealthCare Solution - Right Here


10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.
৳ 0.00
10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.

Products

Payment

Delivery
Indications Used in the treatment and prevention of:
Rheumatoid arthritis
Malaria
Systemic lupus erythematosus (SLE)
Amoebiasis
Administration Should be taken with food.
Adult Dose
Malaria Prevention: 500 mg (300 mg base) orally once weekly
Non-chloroquine-resistant malaria:
1 g (600 mg base) orally, then
500 mg (300 mg base) after 6–8 hours, then
500 mg (300 mg base) at 24 and 48 hours after the initial dose
Amoebiasis (extraintestinal):
1 g (600 mg base) daily for 2 days, then
500 mg (300 mg base) daily for 14–21 days
Child Dose
Malaria Prophylaxis: 5 mg/kg orally once weekly
Treatment:
1st dose: 10 mg/kg orally once
6 hours later: 5 mg/kg orally daily for 2 days
Renal Dose Dose reduction may be required in prolonged treatment for renal impairment.
Contraindications Hypersensitivity, resistant P. falciparum infection, porphyria, retinal damage, concurrent hepatotoxic drugs.
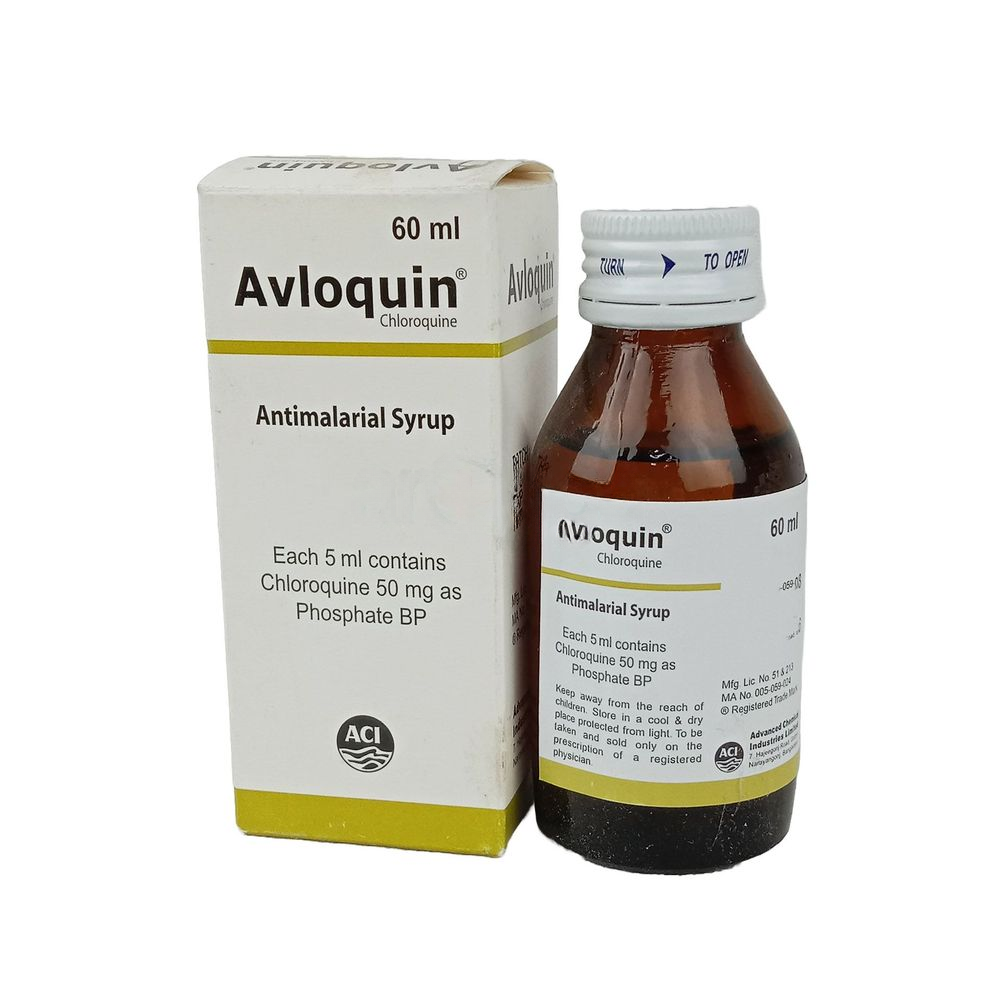
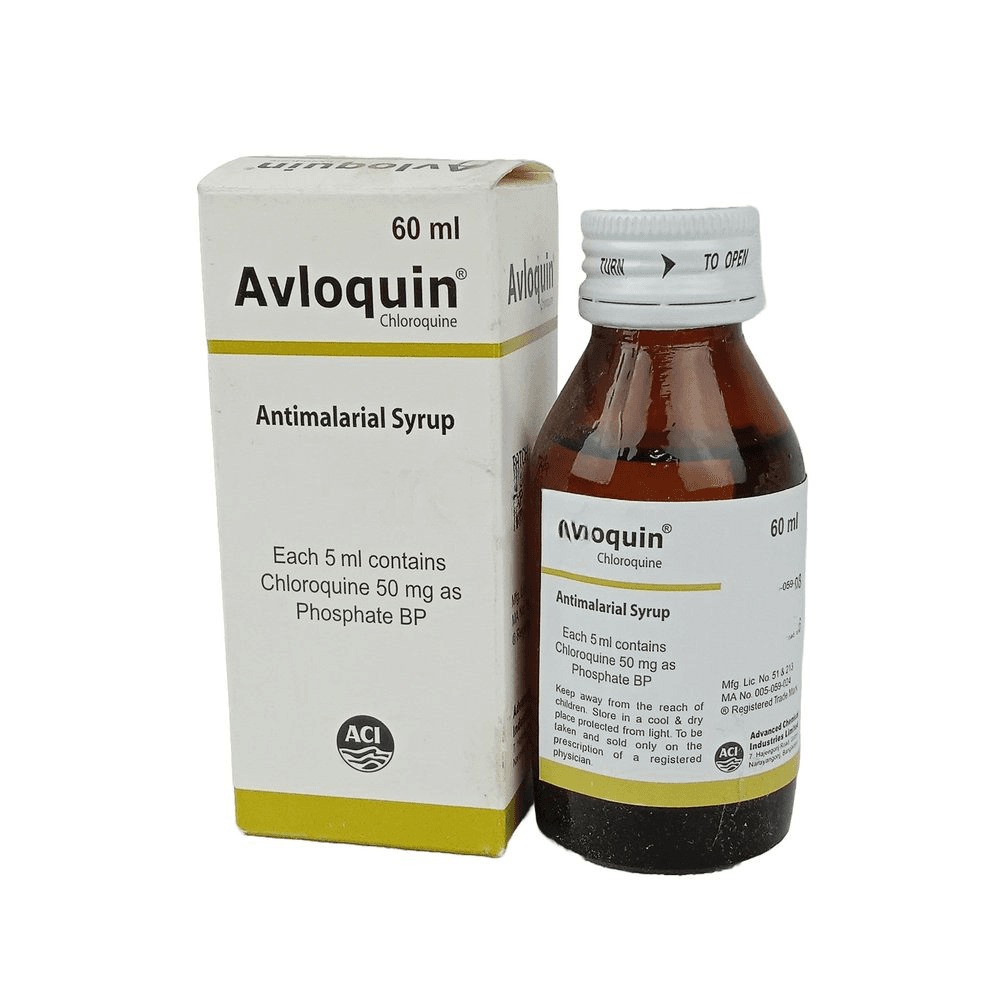
Mode of Action Chloroquine acts on the erythrocytic forms of Plasmodium vivax, P. malariae, and P. falciparum. It increases intravesicular pH in parasite cells, interfering with hemoglobin digestion and nucleoprotein synthesis. It is also effective in extraintestinal amoebiasis and has disease-modifying effects in rheumatoid arthritis and SLE.
Precautions Use with caution in patients with psoriasis, hematologic or CNS disorders, myasthenia gravis, hepatic or renal impairment, G6PD deficiency, epilepsy, and during pregnancy or lactation. Slow IV infusion is recommended to prevent cardiotoxicity. Lactation: Enters breast milk; not recommended.
Side Effects
Common: Nausea, vomiting, diarrhea, loss of appetite, stomach cramps, dizziness, headache, pruritus, urticaria.
Occasional: Retinopathy, hair loss, photosensitivity, tinnitus, myopathy (long-term use).
Rare: Psychosis, seizures, leucopenia, aplastic anemia, hepatitis, hypokalemia, difficulty in visual accommodation.
Potentially Fatal: Cardiac and respiratory arrest, cardiovascular collapse, convulsions, coma.
Pregnancy & Lactation Avoid during pregnancy unless benefits outweigh risks (e.g., malaria prophylaxis). In lactation, discontinue either nursing or drug due to potential infant toxicity.
Drug Interactions
Phenylbutazone: May cause dermatitis.
Neostigmine/Pyridostigmine: Antagonized.
Ampicillin: Reduced bioavailability.
Cimetidine: Raises plasma chloroquine levels.
Halofantrine/Amiodarone: Risk of ventricular arrhythmia.
Mefloquine: Increases risk of convulsions.
Antacids: Reduce absorption; separate by 4 hours.
Pyrimethamine/Sulphadoxine: Rarely causes Stevens–Johnson syndrome.
Quinacrine: Increases toxicity.



Rheumatoid arthritis, Malaria, Systemic lupus erythematosus, SLE, Amoebiasis
Should be taken with food.
Malaria\r\nPrevention: 500 mg (300 mg base) PO once/week\r\n\r\nNon-chloroquine-resistant\r\n1 g (600 mg base) PO, THEN\r\n500 mg (300 mg base) PO 6-8 hours later, THEN\r\n500 mg (300 mg base) PO at 24 hours & 48 hours after initial dose\r\n\r\nAmebiasis, Extraintestinal\r\n1 g (600 mg base) PO qDay for 2 days, THEN\r\n500 mg (300 mg base) qDay for 14-21 days
Malaria\r\nProphylaxis: 5 mg/kg PO q1Week \r\n\r\nTreatment\r\n1st dose: 10 mg/kg PO x1 dose\r\n6 hours after 1st dose: 5 mg/kg PO qDay x2 days
Renal impairment: May need to reduce dose in prolonged treatment.
Hypersensitivity, known or suspected resistant P. falciparum infection, porphyria, retinal damage, concurrent hepatotoxic drugs.
Chloroquine is used for malarial prophylaxis (as a suppressive) and in managing acute attacks of malaria. It is highly active against erythrocytic forms of P. vivax, P. malariae and P. falciparum. It influences Hb digestion by increasing intravesicular pH in malaria parasite cells and interferes with the nucleoprotein synthesis of the patient. It is also effective in extra intestinal amoebiasis. In RA chloroquine and more effectively hydroxychloroquine have a disease-modifying effect.
Psoriasis, diseases of the haematopoietic or CNS systems, myasthenia gravis, hepatic or renal impairment, G6PD deficiency, epilepsy, childn. Pregnancy and lactation. Slow infusion is used upon IV admin to prevent cardiotoxicity.\r\n\r\nLactation: enters breast milk/not recommended
Retinopathy, hair loss, photosensitivity, tinnitus, myopathy (long-term therapy). Diarrhea, Loss of appetite, Nausea, Stomach cramps, Vomiting, Psychosis, seizures, leucopenia and rarely aplastic anaemia, hepatitis, GI upsets, dizziness, hypokalaemia, headache, pruritus, urticaria, difficulty in visual accommodation.\r\n\r\nPotentially Fatal: Cardiac and respiratory arrest, CV collapse, convulsions, coma.
Pregnancy\r\nThere are no adequate and well-controlled studies evaluating the safety and efficacy of chloroquine in pregnant women; usage during pregnancy should be avoided except in prophylaxis or treatment of malaria when benefit outweighs potential risk to fetus\r\n\r\nLactation\r\nBecause of the potential for serious adverse reactions in nursing infants from chloroquine, a decision should be made whether to discontinue nursing or to discontinue drug, taking into account potential clinical benefit of drug to mother
Concomitant therapy with phenylbutazone predisposes to dermatitis, antagonises effect of neostigmine and pyridostigmine, reduces bioavailability of ampicillin. Cimetidine inhibits metabolism of chloroquine raising plasma levels.\r\n\r\nPotentially Fatal: Increased risks of inducing ventricular arrhythmias with halofantrine or other arrhythmogenic drugs eg, amiodarone. Increased risk of convulsions with mefloquine. Antacids reduce absorption of chloroquine hence admin should be separated by 4 hrs. Rarely Stevens-Johnson syndrome, when administered with pyrimethamine/sulphadoxine. Increased toxicity with quinacrine
N/A