Search products by name
Search medicines by name
0
0 item
৳ 0.00
Your Complete HealthCare Solution - Right Here


10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.
৳ 0.00
10657
info@shukhee.com
Telecom Bhaban (Level- 12), 53/1 Box Nagar, Zoo Road, Dhaka-1216.

Products

Payment

Delivery
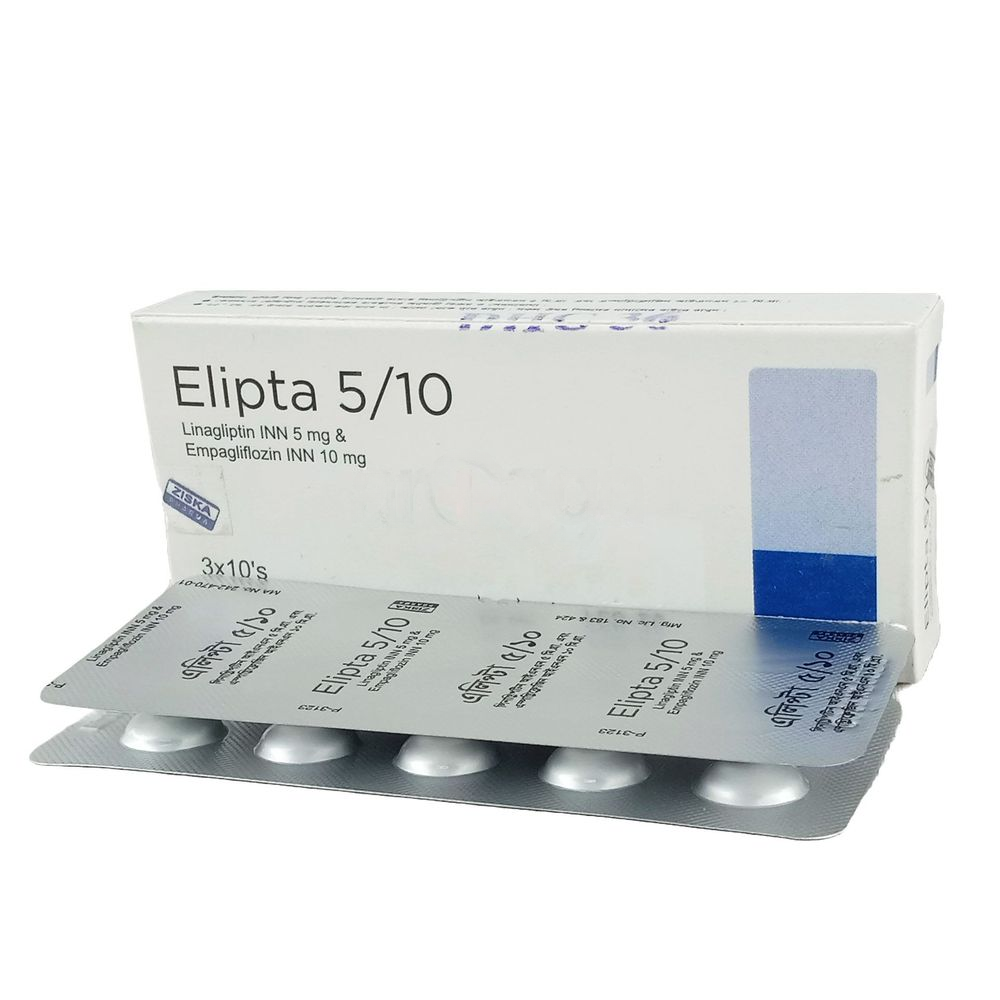
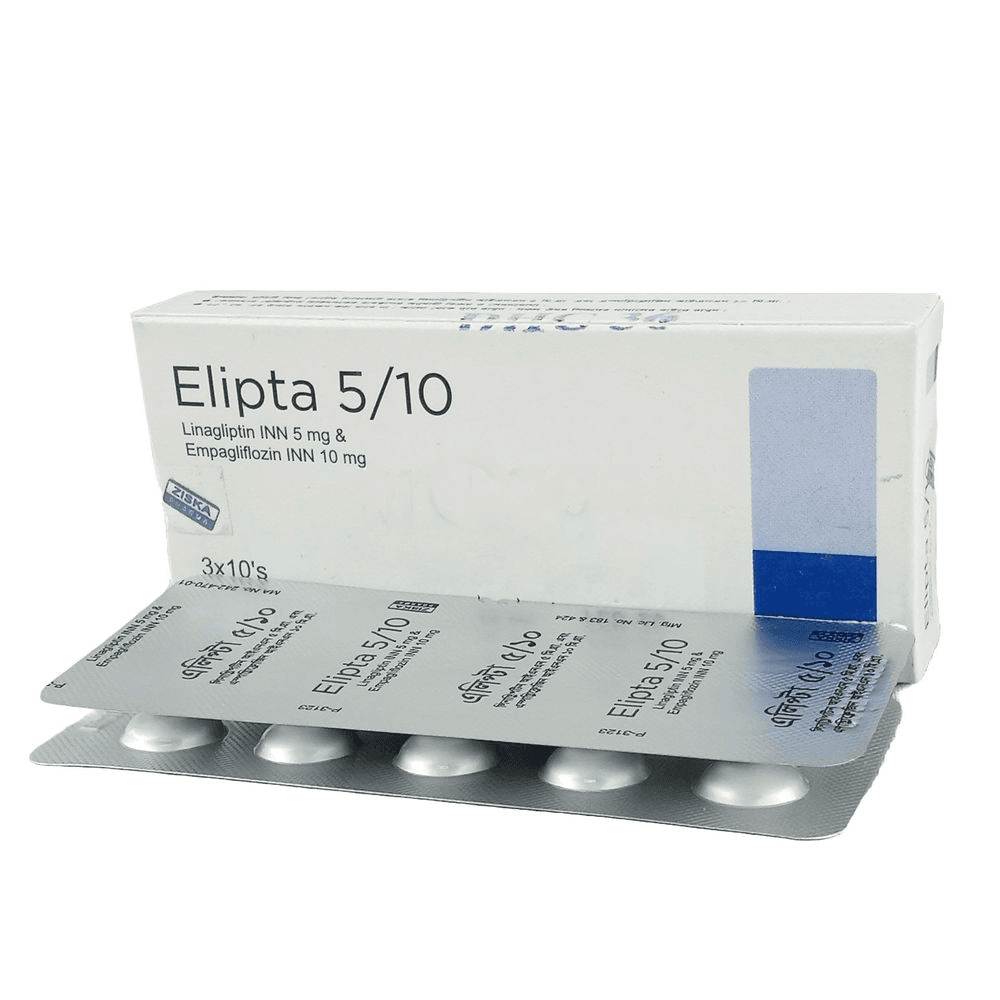
Flipta tablet is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
Linagliptin: Inhibits DPP-4 enzyme, which degrades incretin hormones (GLP-1 and GIP). By increasing active incretin levels, linagliptin stimulates insulin release in a glucose-dependent manner and decreases glucagon secretion, thereby improving glucose homeostasis.
Empagliflozin: Inhibits SGLT2, the main transporter responsible for glucose reabsorption in the kidney. Blocking SGLT2 lowers the renal threshold for glucose, increases urinary glucose excretion, and reduces blood glucose levels.
Recommended dose: 10 mg Empagliflozin + 5 mg Linagliptin once daily, in the morning, with or without food.
Increased dose: May be increased to 25 mg Empagliflozin + 5 mg Linagliptin once daily.
Renal impairment: Assess renal function before initiation. Do not start if eGFR < 45 mL/min/1.73 m². Discontinue if eGFR falls below this threshold.
Diuretics: May increase urine volume and risk of volume depletion.
Insulin/secretagogues: Increased risk of hypoglycemia.
P-gp/CYP3A4 inducers (e.g., Rifampin): May reduce linagliptin exposure and efficacy.
Urine glucose test: Positive due to increased urinary glucose excretion.
1.5-AG assay: Results may be unreliable in patients on SGLT2 inhibitors.
Severe renal impairment, end-stage renal disease, or dialysis.
History of hypersensitivity to linagliptin (e.g., anaphylaxis, angioedema, urticaria, bronchial hyperreactivity).
History of hypersensitivity to empagliflozin.
Pancreatitis, ketoacidosis, volume depletion, pyelonephritis, hypoglycemia (with insulin/secretagogues), Fournier’s gangrene, genital mycotic infections, hypersensitivity reactions, severe arthralgia, bullous pemphigoid, heart failure.
Not recommended during the 2nd and 3rd trimesters. Limited data in pregnancy; risks cannot be excluded. Poorly controlled diabetes itself poses risks to mother and fetus.
Use caution in patients with pancreatitis, hypotension, ketoacidosis, renal impairment, urosepsis, pyelonephritis, hypoglycemia, genital infections, hypersensitivity.
Pancreatitis: Reported with linagliptin.
Ketoacidosis: Rare but serious, reported with SGLT2 inhibitors including empagliflozin.
Volume depletion: May cause hypotension or transient renal changes.
UTIs: Increased risk with SGLT2 inhibitors.
Fournier’s gangrene: Rare necrotizing infection requiring urgent surgery.
Heart failure: Observed with some DPP-4 inhibitors.
Supportive management: gastric lavage, monitoring, symptomatic treatment. Hemodialysis unlikely to remove linagliptin or empagliflozin effectively.
Antidiabetic agent (DPP-4 inhibitor + SGLT2 inhibitor combination).


N/A
N/A