Search products by name
Search medicines by name
0
0 item
৳ ০.০০
আপনার সব স্বাস্থ্যসেবার সমাধান — এখন এক জায়গাতেই


১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬
৳ ০.০০
১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬

Quantity:

Products

Payment

Delivery
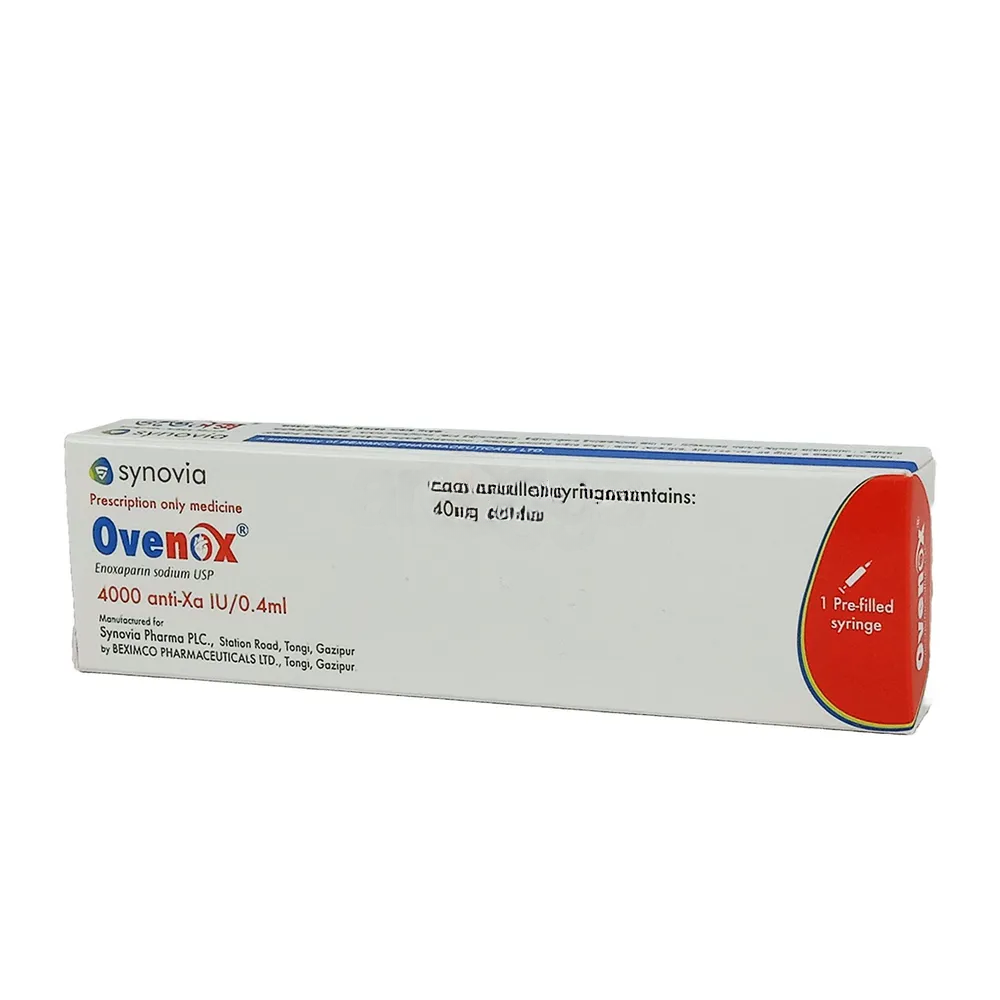
Myocardial infarction, Unstable angina, Venous thromboembolism, Deep vein thrombosis
Low body weight (<45 kg for women or <57 kg for men): Increased exposure has been observed with prophylactic (non-weight adjusted) dosage; carefully monitor for sign/symptoms of bleeding\r\n\r\nAdminister deep SC alternating right and left anterior and posterior abdominal walls into skin fold held between thumb and forefinger\r\n\r\nUse of tuberculin syringe (or equivalent) is recommended to assure appropriate measurement of dose\r\n\r\nFor IV administration, may administer in IV line with 0.9% NaCl or D5W
$4e
Renal impairment\r\nSevere (CrCl <30 mL/min): Dosage reductions required\r\nProphylaxis in abdominal surgery: 30 mg SC qDay\r\nProphylaxis in hip or knee replacement surgery: 30 mg SC qDay\r\nProphylaxis in medical patients with restricted mobility: 30 mg SC qDay\r\nDVT treatment (inpatient or outpatient) coadministered with warfarin: 1 mg/kg SC qDay\r\nNon-Q-wave myocardial infarction: 1 mg/kg SC qDay\r\nTreatment of acute STEMI (<75 years): 30 mg IV single bolus plus 1 mg/kg SC, THEN 1 mg/kg SC qDay\r\nTreatment of acute STEMI (>75 years): No initial bolus; maintenance of 1 mg/kg SC qDay
Hyper-sensitivity to either Enoxaparin, heparin or other low molecular weight heparins; major clotting disorders like history of thrombocytopenia, active gastro-intestinal ulcer or organic lesion likely to bleed, recent haemorrhagic vascular cerebral stroke. Although rare, cutaneous or systemic allergic reactions may occur.
Enoxaparin is a low molecular weight heparin w/ anticoagulant properties. It acts by enhancing the inhibition rate of activated clotting factors including thrombin and factor Xa through its action on antithrombin III.
Enoxaparin injection should not be administered by intramuscular route. Enoxaparin should be used with caution in conditions with increased potential for bleeding, such as impaired hemostasis, history of peptic ulcer, recent ischemic stroke, uncontrolled severe arterial hypertension, diabetic retinopathy, recent neuro or opthalmologic surgery and low weight patients. It is recommended that the platelet count be measured befored the initiation of the treatment and regularly thereafter during treatment.\r\n\r\nLactation: Excretion in milk unknown; not recommended
1-10%\r\nHemorrhage (1-4%),Elevation of serum aminotransferases (6%),Fever (5-8%),Local site reactions (2-5%),Thrombocytopenia (3%),Nausea (3%),Anemia (2%),Ecchymosis (3%)\r\n\r\n<1%\r\nAtrial fibrillation,Heart failure,Pulmonary edema,Pneumonia\r\n\r\nPotentially Fatal: Haemorrhagic complications.
$4f
Increased risk of bleeding w/ anticoagulants, platelet aggregation inhibitors (e.g. dipyridamole, salicylates, NSAIDs, sulfinpyrazone). May increase bleeding w/ vit E.
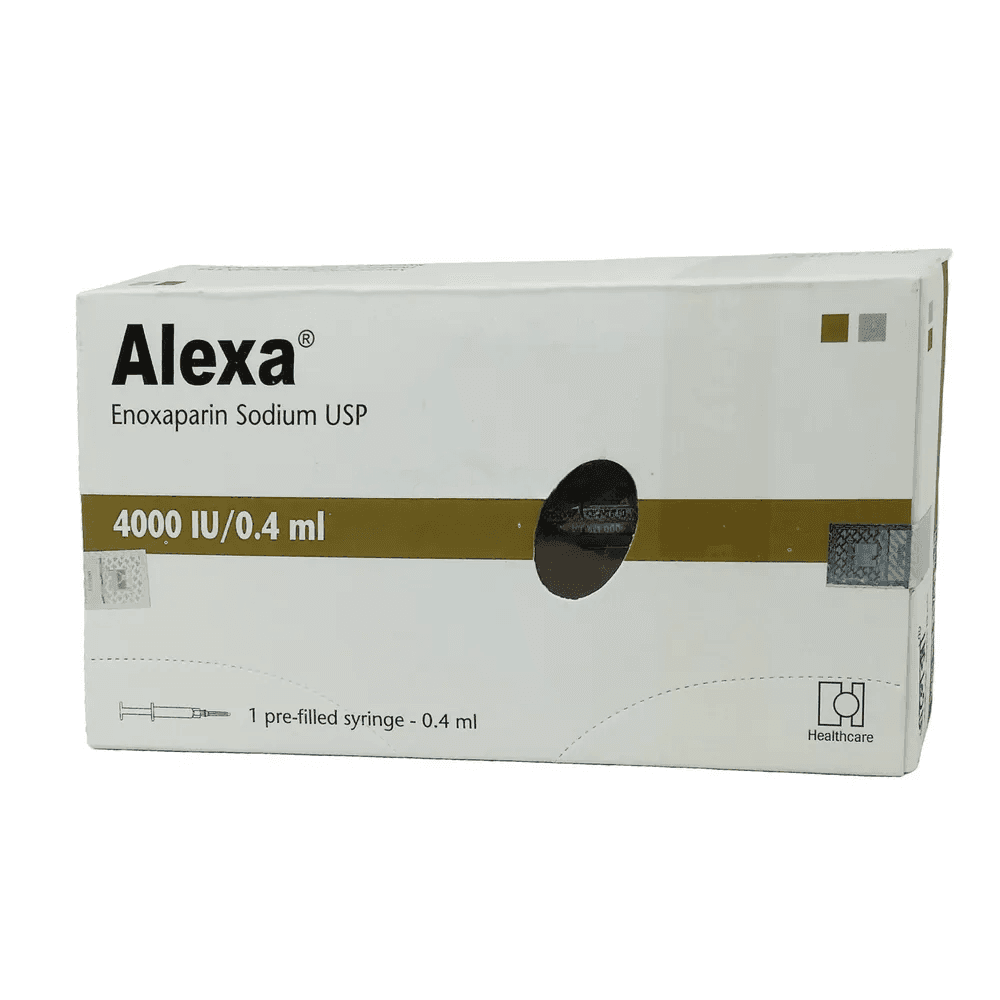
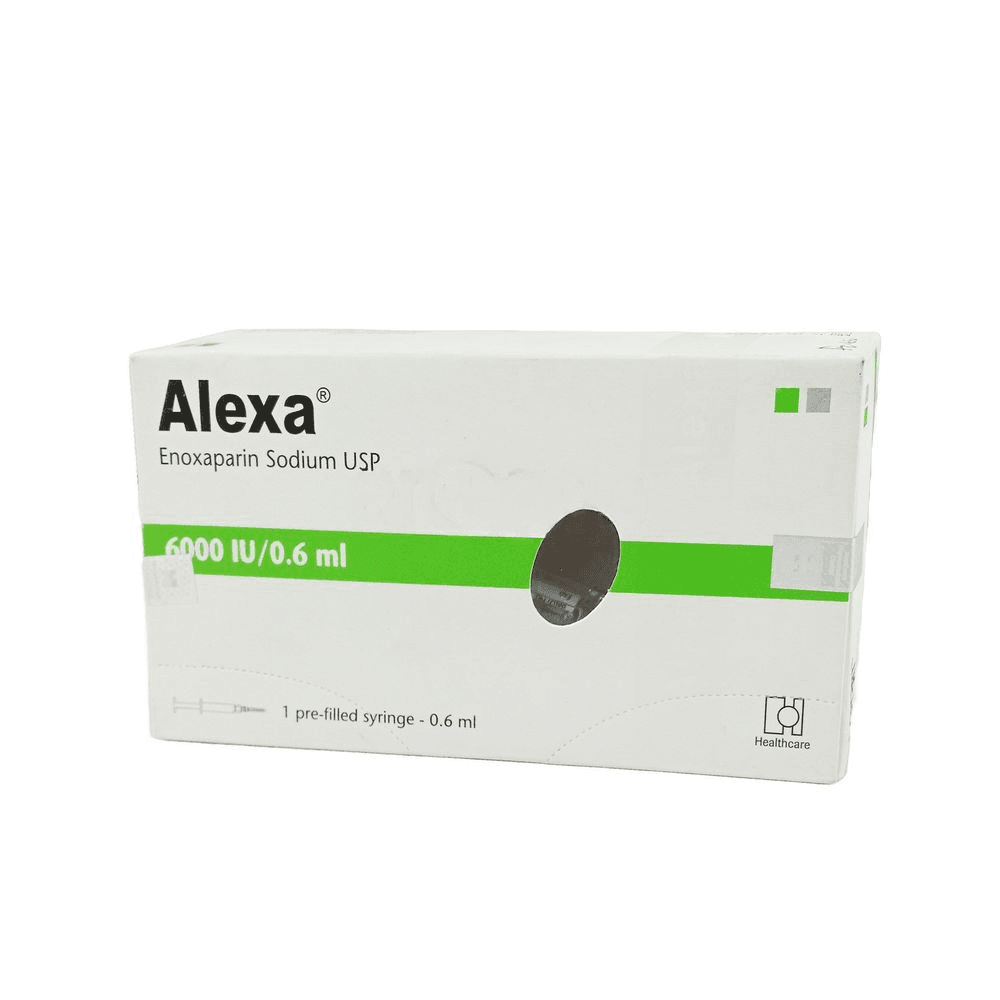
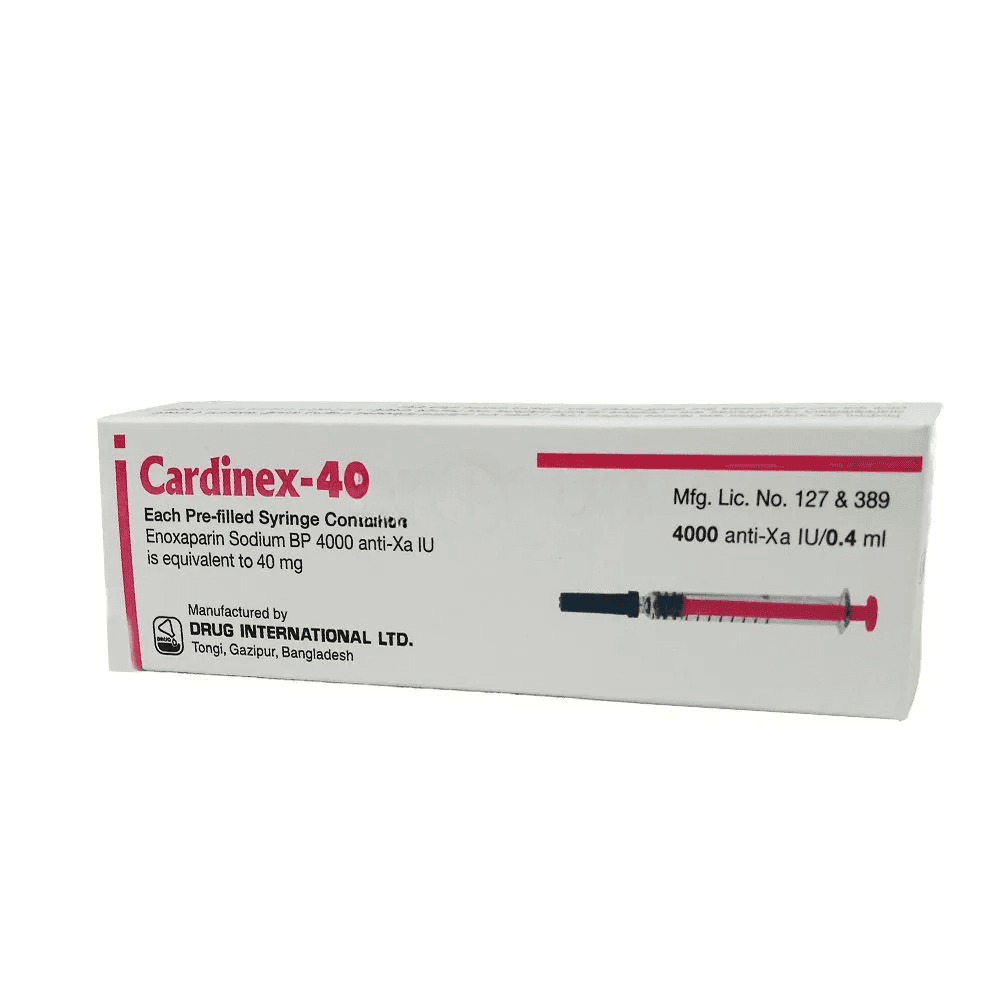
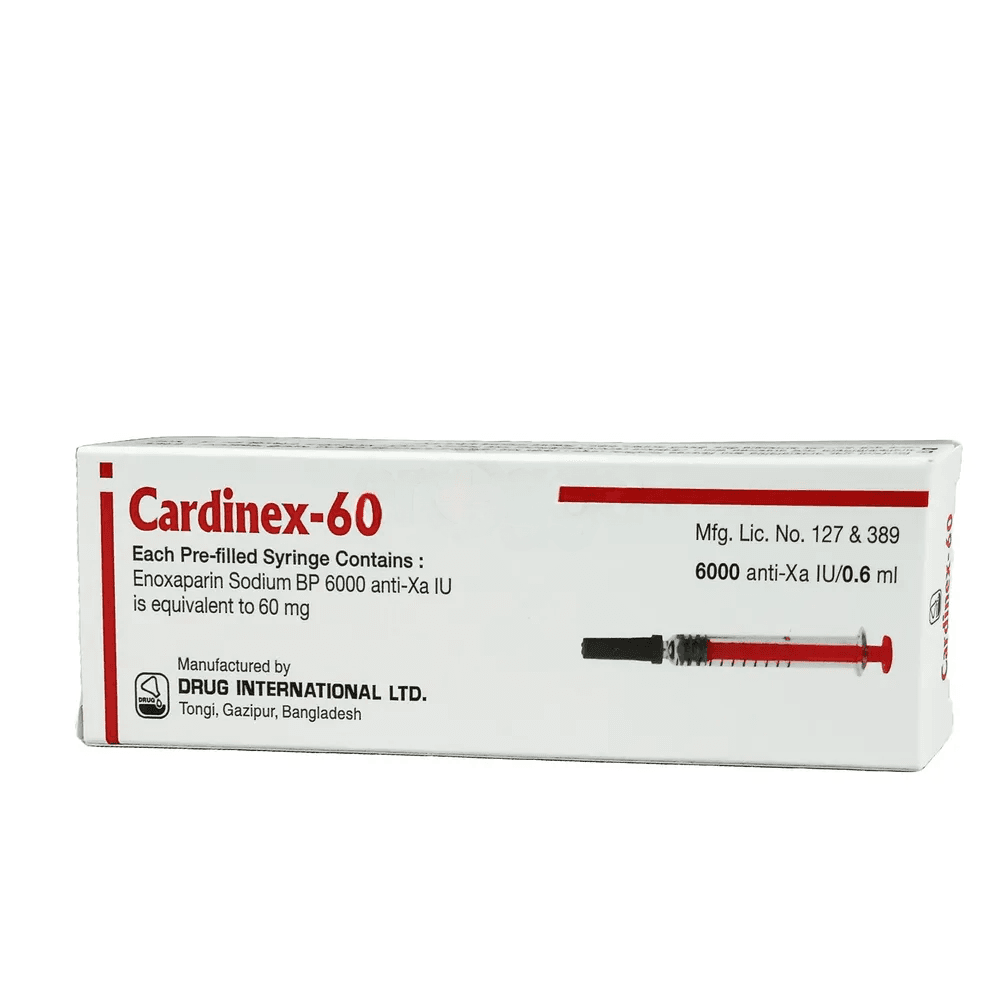
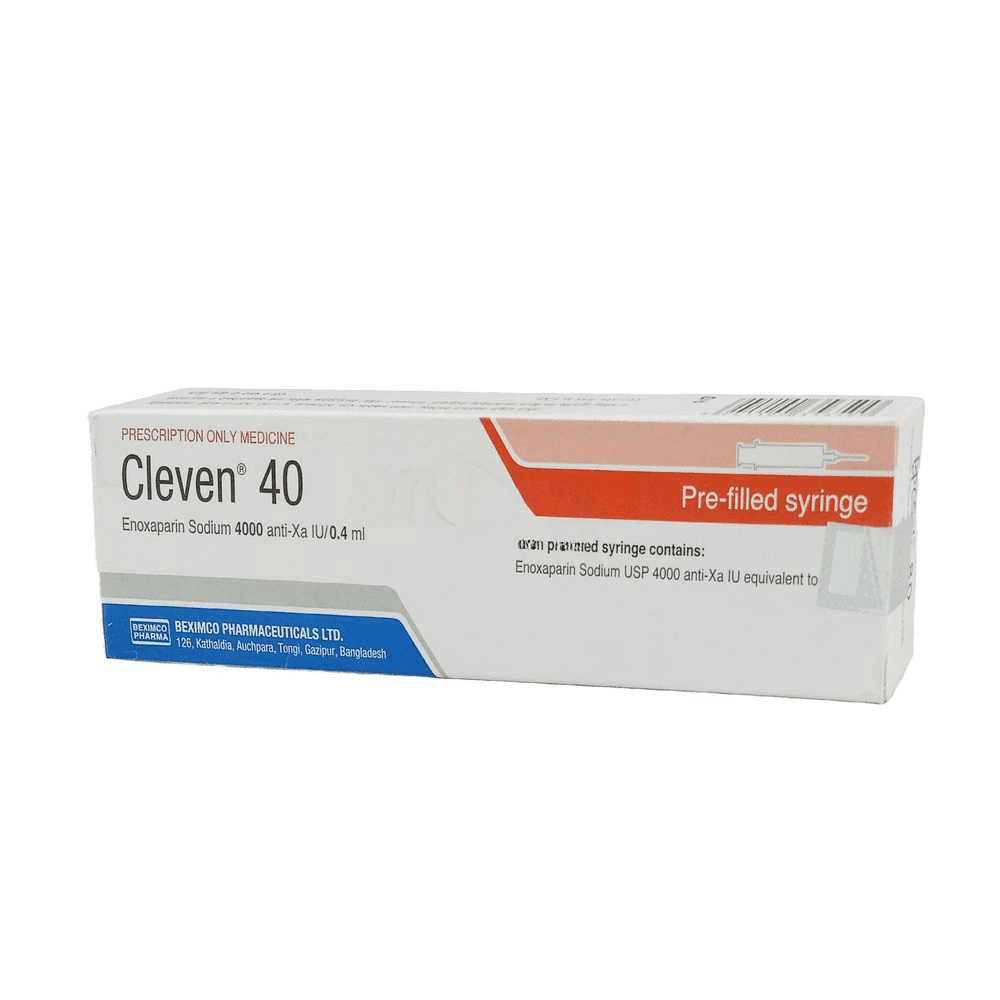
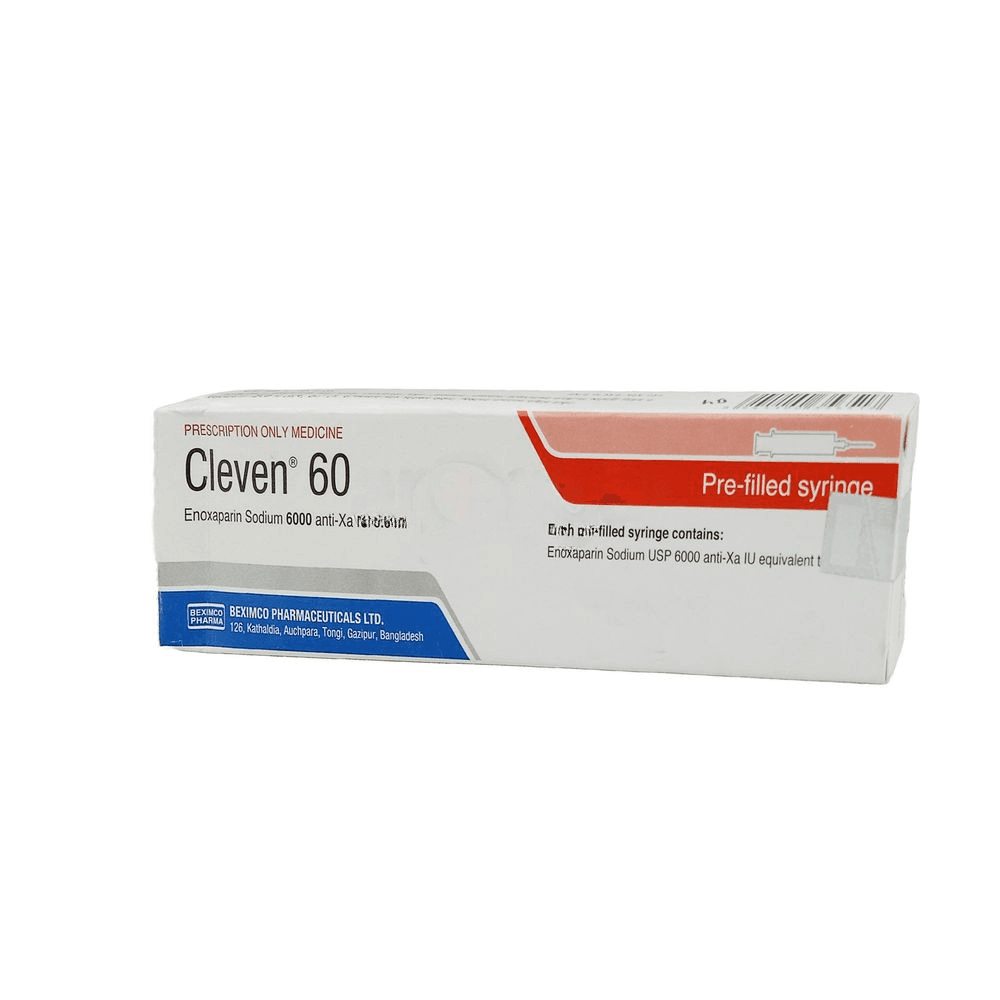
Myocardial infarction, Unstable angina, Venous thromboembolism, Deep vein thrombosis
Low body weight (<45 kg for women or <57 kg for men): Increased exposure has been observed with prophylactic (non-weight adjusted) dosage; carefully monitor for sign/symptoms of bleeding\r\n\r\nAdminister deep SC alternating right and left anterior and posterior abdominal walls into skin fold held between thumb and forefinger\r\n\r\nUse of tuberculin syringe (or equivalent) is recommended to assure appropriate measurement of dose\r\n\r\nFor IV administration, may administer in IV line with 0.9% NaCl or D5W
$4e
Renal impairment\r\nSevere (CrCl <30 mL/min): Dosage reductions required\r\nProphylaxis in abdominal surgery: 30 mg SC qDay\r\nProphylaxis in hip or knee replacement surgery: 30 mg SC qDay\r\nProphylaxis in medical patients with restricted mobility: 30 mg SC qDay\r\nDVT treatment (inpatient or outpatient) coadministered with warfarin: 1 mg/kg SC qDay\r\nNon-Q-wave myocardial infarction: 1 mg/kg SC qDay\r\nTreatment of acute STEMI (<75 years): 30 mg IV single bolus plus 1 mg/kg SC, THEN 1 mg/kg SC qDay\r\nTreatment of acute STEMI (>75 years): No initial bolus; maintenance of 1 mg/kg SC qDay
Hyper-sensitivity to either Enoxaparin, heparin or other low molecular weight heparins; major clotting disorders like history of thrombocytopenia, active gastro-intestinal ulcer or organic lesion likely to bleed, recent haemorrhagic vascular cerebral stroke. Although rare, cutaneous or systemic allergic reactions may occur.
Enoxaparin is a low molecular weight heparin w/ anticoagulant properties. It acts by enhancing the inhibition rate of activated clotting factors including thrombin and factor Xa through its action on antithrombin III.
Enoxaparin injection should not be administered by intramuscular route. Enoxaparin should be used with caution in conditions with increased potential for bleeding, such as impaired hemostasis, history of peptic ulcer, recent ischemic stroke, uncontrolled severe arterial hypertension, diabetic retinopathy, recent neuro or opthalmologic surgery and low weight patients. It is recommended that the platelet count be measured befored the initiation of the treatment and regularly thereafter during treatment.\r\n\r\nLactation: Excretion in milk unknown; not recommended
1-10%\r\nHemorrhage (1-4%),Elevation of serum aminotransferases (6%),Fever (5-8%),Local site reactions (2-5%),Thrombocytopenia (3%),Nausea (3%),Anemia (2%),Ecchymosis (3%)\r\n\r\n<1%\r\nAtrial fibrillation,Heart failure,Pulmonary edema,Pneumonia\r\n\r\nPotentially Fatal: Haemorrhagic complications.
$4f
Increased risk of bleeding w/ anticoagulants, platelet aggregation inhibitors (e.g. dipyridamole, salicylates, NSAIDs, sulfinpyrazone). May increase bleeding w/ vit E.
N/A