Search products by name
Search medicines by name
0
0 item
৳ ০.০০
আপনার সব স্বাস্থ্যসেবার সমাধান — এখন এক জায়গাতেই


১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬
৳ ০.০০
১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬

Quantity:

Products

Payment

Delivery
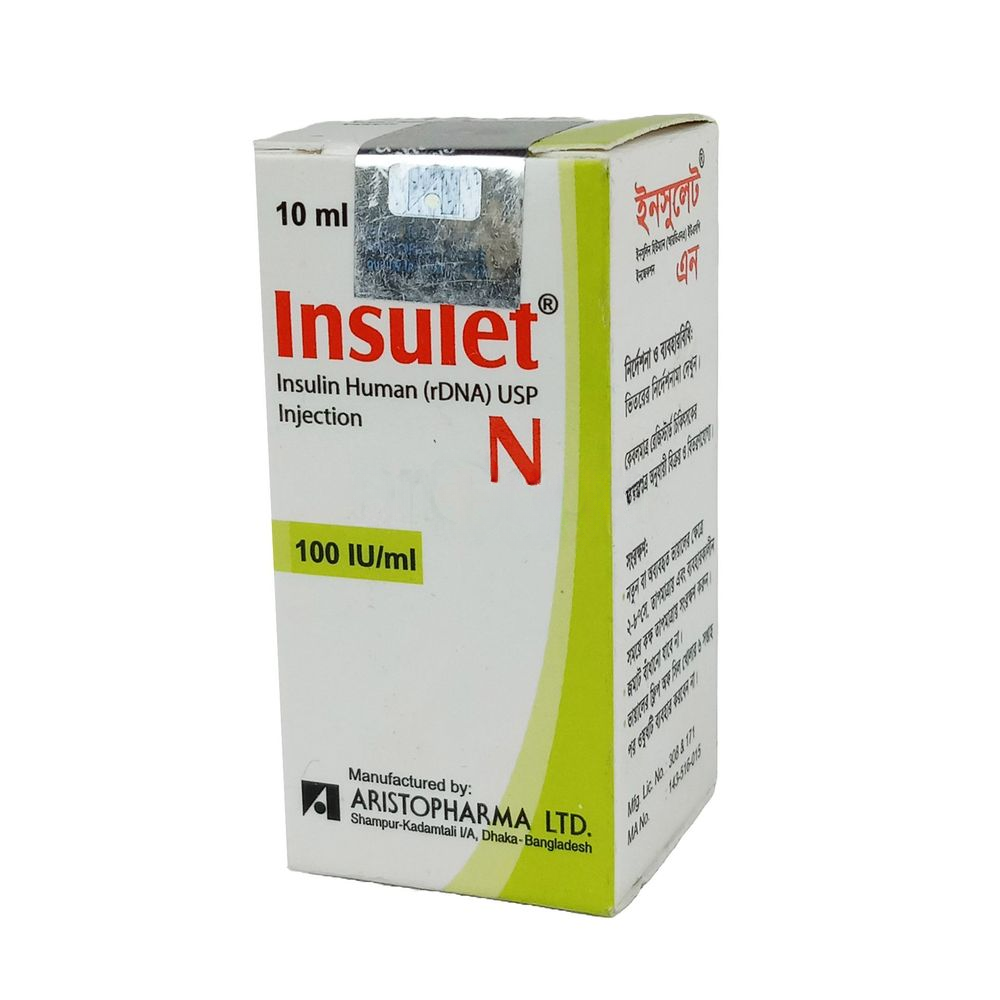
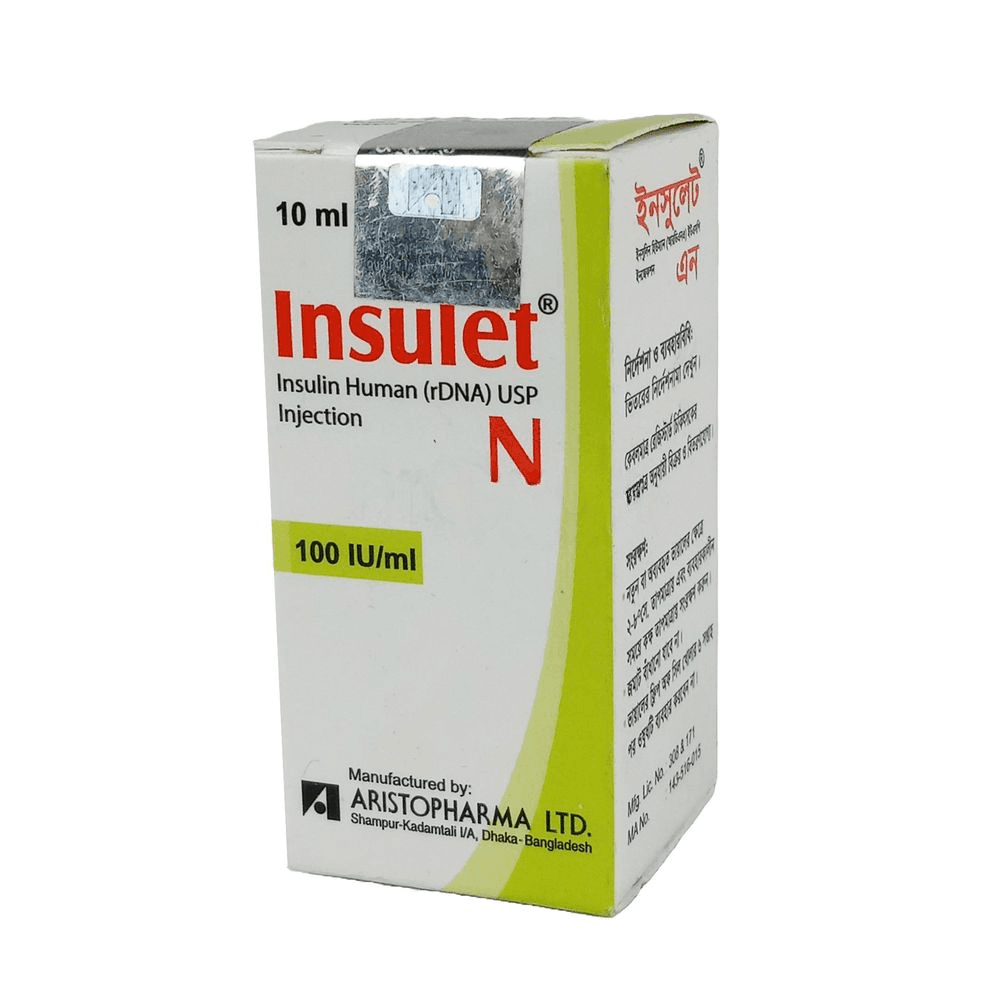
Diabetes mellitus
Administer within 15 minutes before a meal or immediately after a meal. \r\nAdminister subcutaneously in the upper arm, thigh or abdominal wall. A subcutaneous injection into the abdominal wall results in a faster absorption than from other injection sites.\r\nNPH Insulin suspensions are never to be administered intravenously.
Type 1 Diabetes Mellitus\r\n<12 years: Safety and efficacy not established\r\n\r\n>12 years: Suggested dose is 0.5-1 unit/kg/day SC; use adult dosing; \r\nusual daily maintenance range in adolescents is <1.2 units/kg/day during growth spurts
Renal impairment: Dose adjustments may be needed.
Hypoglycaemia. Hypersensitivity to any of the components.
Pregnancy (insulin requirements tend to fall during the 1st trimester, increase during the 2nd and 3rd) and lactation. Caution with decreased insulin requirements: Diarrhea, nausea/vomiting, malabsorption, hypothyroidism, renal impairment, hepatic impairment\r\nHypokalemia may occur\r\nNot for IV or IM administration\r\nUse with caution in renal and hepatic impairment (dosage requirements may be reduced)\r\nCaution with increased insulin requirements: Fever, hyperthyroidism, trauma, infection, surgery\r\n\r\nLactation: Safe to use while breastfeeding
Allergic reactions. Injection site reaction, lipodystrophy, pruritus, rash, lipoatrophy, hypokalaemia, blurred vision. Hypoglycaemia, insulin resistance
Possible absence of hypoglycaemic warning symptoms with beta-blockers. Decreased hypoglycaemic effect with corticosteroids, danazol, diazoxide, diuretics, glucagon, isoniazid, phenothiazine derivatives, somatropin, sympathomimetic agents, thyroid hormones, oestrogens, progestins (e.g. in oral contraceptives), protease inhibitors and atypical antipsychotic (e.g. olanzapine and clozapine). Increased hypoglycaemic effect with oral antidiabetic agents, ACE inhibitors, disopyramide, fibrates, fluoxetine, MAOIs, pentoxifylline, propoxyphene, salicylates and sulfonamide antibiotics. Decreased insulin resistance with octreotide and lanreotide. Increased risk of wt gain and peripheral oedema with pioglitazone, rosiglitazone. Decreased effect of sermorelin.
Diabetes mellitus
Administer within 15 minutes before a meal or immediately after a meal. \r\nAdminister subcutaneously in the upper arm, thigh or abdominal wall. A subcutaneous injection into the abdominal wall results in a faster absorption than from other injection sites.\r\nNPH Insulin suspensions are never to be administered intravenously.
$4e
Type 1 Diabetes Mellitus\r\n<12 years: Safety and efficacy not established\r\n\r\n>12 years: Suggested dose is 0.5-1 unit/kg/day SC; use adult dosing; \r\nusual daily maintenance range in adolescents is <1.2 units/kg/day during growth spurts
Renal impairment: Dose adjustments may be needed.
Hypoglycaemia. Hypersensitivity to any of the components.
$4f
Pregnancy (insulin requirements tend to fall during the 1st trimester, increase during the 2nd and 3rd) and lactation. Caution with decreased insulin requirements: Diarrhea, nausea/vomiting, malabsorption, hypothyroidism, renal impairment, hepatic impairment\r\nHypokalemia may occur\r\nNot for IV or IM administration\r\nUse with caution in renal and hepatic impairment (dosage requirements may be reduced)\r\nCaution with increased insulin requirements: Fever, hyperthyroidism, trauma, infection, surgery\r\n\r\nLactation: Safe to use while breastfeeding
Allergic reactions. Injection site reaction, lipodystrophy, pruritus, rash, lipoatrophy, hypokalaemia, blurred vision. Hypoglycaemia, insulin resistance
Possible absence of hypoglycaemic warning symptoms with beta-blockers. Decreased hypoglycaemic effect with corticosteroids, danazol, diazoxide, diuretics, glucagon, isoniazid, phenothiazine derivatives, somatropin, sympathomimetic agents, thyroid hormones, oestrogens, progestins (e.g. in oral contraceptives), protease inhibitors and atypical antipsychotic (e.g. olanzapine and clozapine). Increased hypoglycaemic effect with oral antidiabetic agents, ACE inhibitors, disopyramide, fibrates, fluoxetine, MAOIs, pentoxifylline, propoxyphene, salicylates and sulfonamide antibiotics. Decreased insulin resistance with octreotide and lanreotide. Increased risk of wt gain and peripheral oedema with pioglitazone, rosiglitazone. Decreased effect of sermorelin.
N/A