Search products by name
Search medicines by name
0
0 item
৳ ০.০০
আপনার সব স্বাস্থ্যসেবার সমাধান — এখন এক জায়গাতেই


১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬
৳ ০.০০
১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬



Quantity:

Products

Payment

Delivery
Indications Obeliva tablet is indicated for adult patients with primary biliary cholangitis (PBC) without cirrhosis or with compensated cirrhosis who show no evidence of portal hypertension. It may be used in combination with ursodeoxycholic acid (UDCA) when response to UDCA is inadequate, or as monotherapy in patients unable to tolerate UDCA.
Pharmacology Obeticholic acid acts as a Farnesoid X Receptor (FXR) agonist, regulating bile‑acid, inflammatory, fibrotic, and metabolic pathways. FXR activation reduces hepatocyte bile‑acid concentration by suppressing synthesis from cholesterol and increasing bile‑acid transport out of hepatocytes, thereby limiting bile‑acid pool size and promoting choleresis.
Dosage & Administration
Starting dose: 5 mg once daily for 3 months.
If inadequate response: increase to 10 mg once daily.
Monitor: biochemical response, bilirubin, prothrombin time, and signs of portal hypertension.
Discontinue: if hepatic decompensation, portal hypertension, or biliary obstruction develops.
Pruritus management: add antihistamine or bile‑acid‑binding resin, reduce dose, or temporarily interrupt therapy.
Interaction
Bile‑acid binding resins reduce absorption; take Obeliva ≥ 4 hours apart.
Warfarin: monitor INR.
CYP1A2 substrates: monitor drugs like theophylline or tizanidine.
Avoid BSEP inhibitors (e.g., cyclosporine).
Contraindications
Decompensated cirrhosis (Child‑Pugh B or C)
Compensated cirrhosis with portal hypertension
Complete biliary obstruction
Side Effects Common: pruritus, fatigue, abdominal pain, rash, arthralgia, dizziness, constipation, abnormal thyroid function, eczema.
Pregnancy & Lactation Limited human data; animal studies show no fetal harm. Unknown if excreted in breast milk—use only if clinically needed.
Precautions & Warnings
Risk of hepatic decompensation or failure in PBC patients with cirrhosis.
Severe pruritus may occur; manage with dose adjustment or temporary interruption.
Monitor HDL‑C levels; dose‑dependent reductions observed.
Use in Special Populations
Pediatric: not established.
Geriatric: no major differences, but greater sensitivity possible.
Hepatic impairment: contraindicated in decompensated cirrhosis or portal hypertension.
Overdose Effects High doses (25–50 mg) may cause hepatic adverse reactions such as ascites, jaundice, and portal hypertension; observe and provide supportive care.

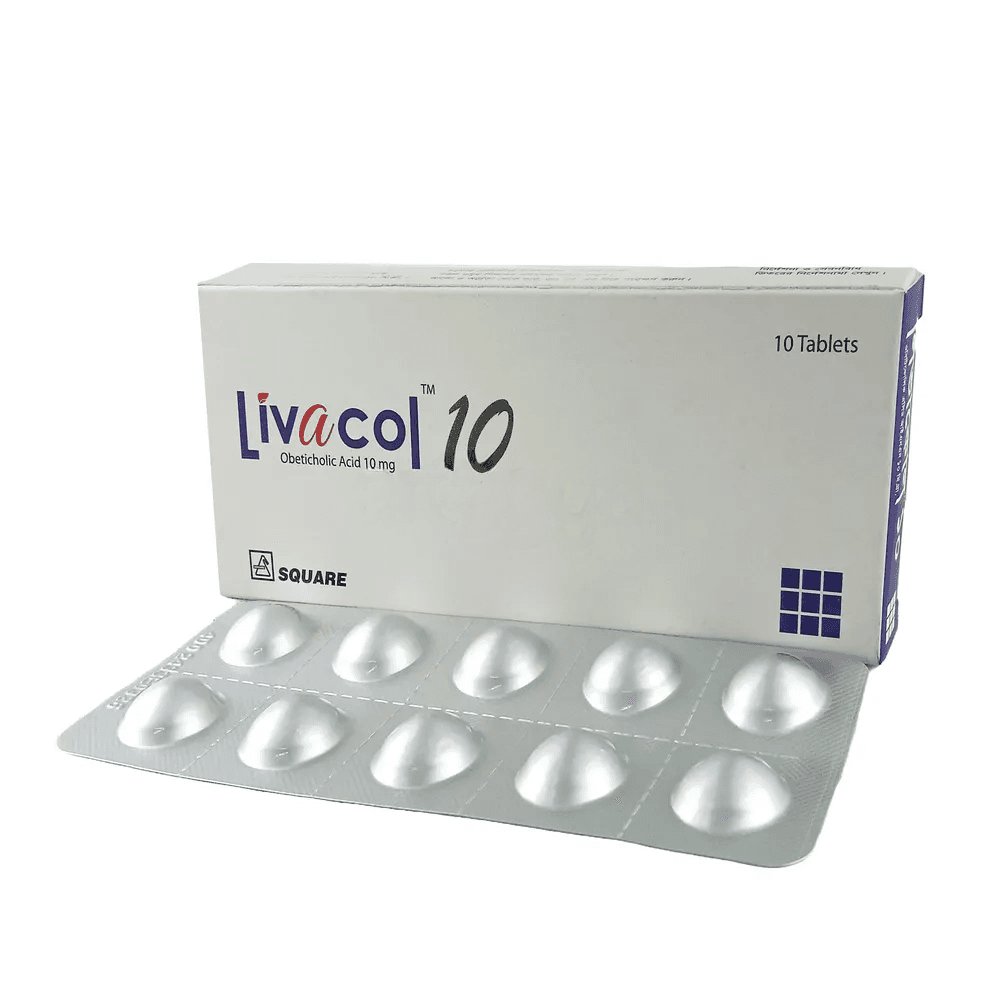
Primary Biliary Cholangitis\r\nIndicated for primary biliary cholangitis (PBC), in combination with ursodeoxycholic acid (UDCA) in adults with an inadequate response to UDCA for at least 1 yr or as monotherapy in adults unable to tolerate UDCA
May take with or without food\r\n\r\nConcomitant bile-acid binding resin: Separate obeticholic acid dose by at least 4 hr
$4e
Complete biliary obstruction
Farnesoid X receptor (FXR) agonist\r\n\r\nFXR is a nuclear receptor expressed in the liver, intestine, kidney, and adipose tissue that regulates a wide variety of target genes critically involved in the control of bile acid synthesis and transport, lipid metabolism, and glucose homeostasis\r\n\r\nFXR activation suppresses de novo synthesis of bile acids in hepatocytes as well as increasing transport of bile acids out of hepatocytes, thereby reducing exposure of the hepatocytes to bile acid
Hepatic decompensation and failure, in some cases fatal, reported in patients with PBC who have decompensated cirrhosis or Child-Pugh Class B or C hepatic impairment when obeticholic acid was dosed more frequently than the recommended starting dosage of 5 mg once weekly\r\n\r\nMonitor patients for elevations in liver enzymes and risks for hepatic decompensation (eg, worsening renal function, dehydration)\r\n\r\nDose response relationship observed in clinical trials for liver-related adverse reactions, including jaundice, worsening ascites, and primary biliary cholangitis flare (doses >10 mg/day)\r\n\r\nLactation\r\nUnknown if distributed in human breast milk\r\n\r\nConsider the developmental and health benefits of breastfeeding along with the mother’s clinical need for the drug, and any potential adverse effects on the breastfed infant from the drug or from the underlying maternal condition\r\n
>10%\r\nPruritus (56-70%)\r\nFatigue (19-25%)\r\nSevere pruritus (19-23%)\r\nReduced HDL-C (9-20%)\r\nAbdominal pain and discomfort (10-19%)\r\n\r\n1-10%\r\nRash (7-10%)\r\nOropharyngeal pain (7-8%)\r\nDizziness (7%)\r\nConstipation (7%)\r\nPeripheral edema (3-7%)\r\nPalpitations (3-7%)\r\nPyrexia (7%)\r\nThyroid function abnormality (4-6%)\r\nEczema (3-6%)\r\n\r\n
Bile-acid binding resins may reduce the absorption, systemic exposure, and efficacy of obeticholic acid\r\nCoadministration of warfarin and obeticholic acid has been shown to decrease the INR; monitor the INR and adjust warfarin dose accordingly\r\nCoadministration with CYP1A2 substrates (eg, theophylline, tizanidine) may increase exposure of CYP1A2 substrates; monitor CYP1A2 substrates with narrow therapeutic index\r\nAvoid concomitant use of inhibitors of the bile salt efflux pump (BSEP) (eg, cyclosporine); BSEP inhibitors may exacerbate accumulation of conjugated bile salts in the liver and result in clinical symptoms
N/A