Search products by name
Search medicines by name
0
0 item
৳ ০.০০
আপনার সব স্বাস্থ্যসেবার সমাধান — এখন এক জায়গাতেই


১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬
৳ ০.০০
১০৬৫৭
info@shukhee.com
টেলিকম ভবন, ৫৩/১, বক্স নগর, ঢাকা-১২১৬

Products

Payment

Delivery
Diabetes mellitus
Administer SC BID (ie, before breakfast and evening meal); each dose intended to cover 2 meals or a meal and snack\r\nInject SC into abdominal wall, thigh, or upper arm
Subcutaneous\r\nDiabetes Mellitus\r\nCombination rapid-onset (faster than regular insulin) and intermediate-acting insulins in fixed dose\r\nDose regimen varies among patients depending on metabolic needs; typical daily insulin requirements range between 0.5-1 unit/kg\r\nInitially, 10 units with the largest meal of the day, dose adjustments may be made on a wkly basis according to blood glucose levels. \r\nDose should not be increased if there is hypoglycaemic episode (<70 mg/dl) during a 3-day period.
Safety and efficacy not established
Renal impairment: Dose adjustments may be required.
Hypoglycaemia. Hypersensitivity to any of the components.
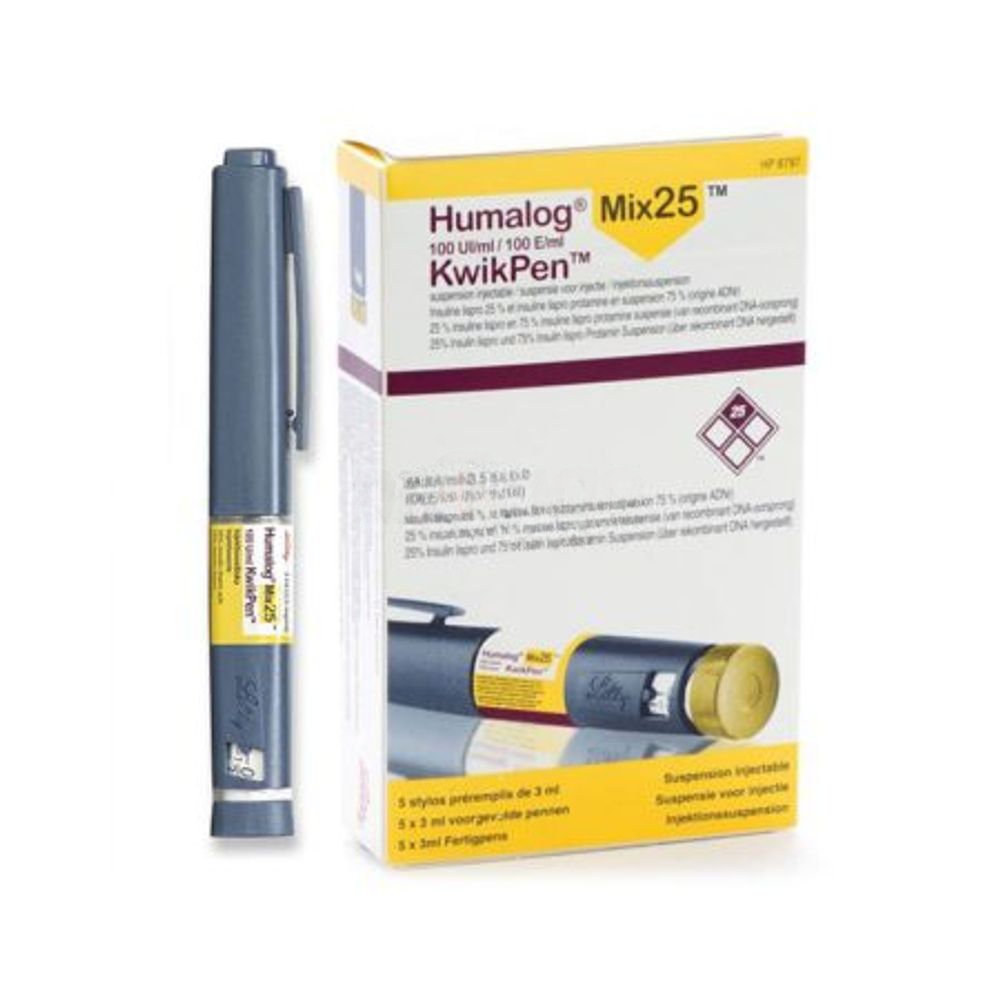
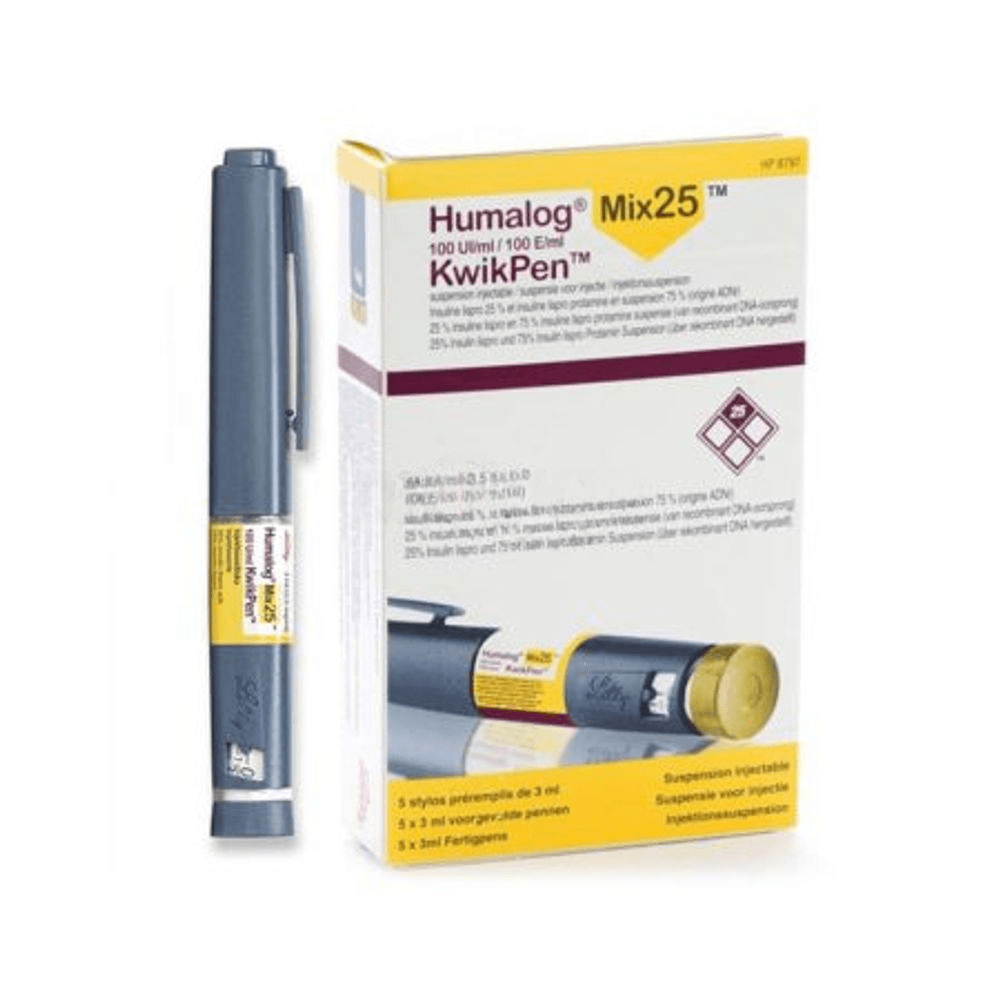
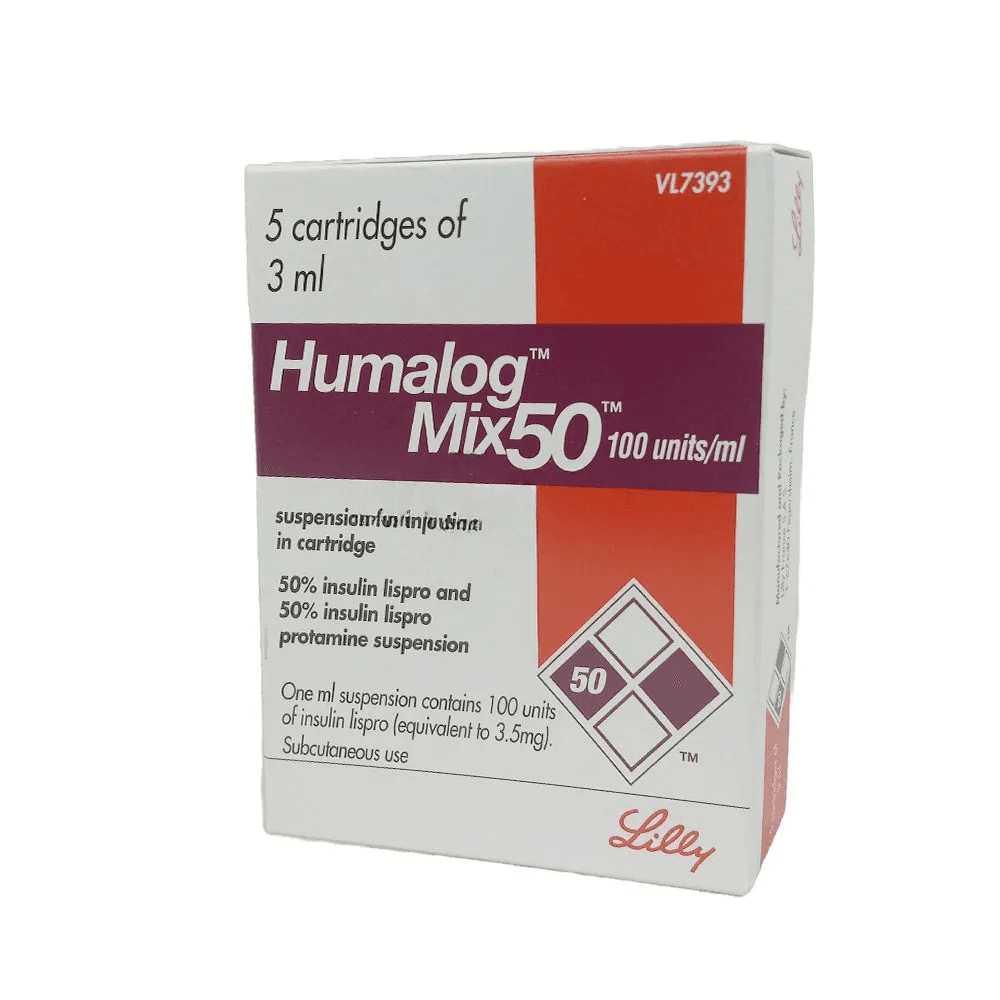
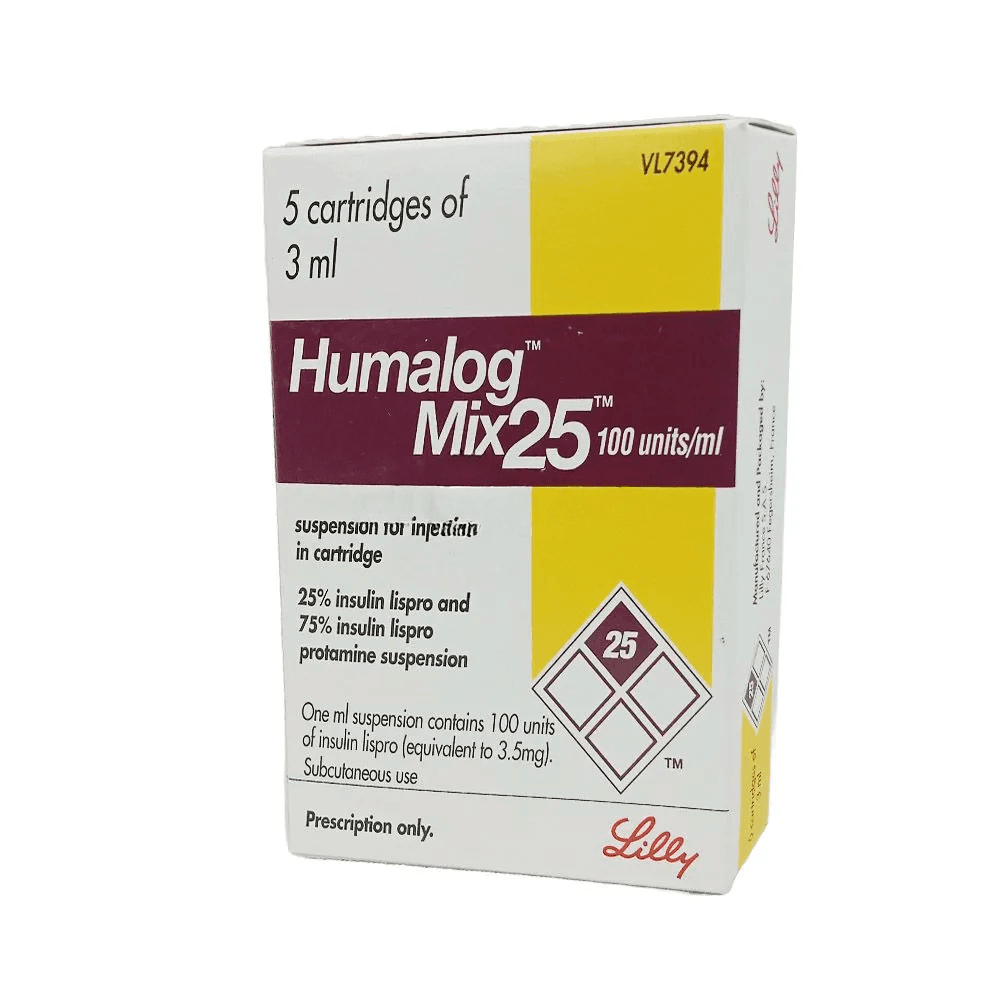
Insulin lispro is a short-acting biosynthetic human insulin analogue. Insulin lispro protamine is an intermediate-acting glucose-lowering agent; it is a suspension of crystals produced from combining insulin lispro and protamine sulfate under appropriate conditions for crystal formation. They are used together for the regulation of glucose metabolism.
Renal or hepatic impairment; pregnancy, lactation; transferring from other insulin. Monitor serum glucose, potassium, electrolytes, HbA1c and lipid profile. Concomitant illness esp infections.\r\n\r\nLactation: Unknown whether distributed in breast milk; compatible with breast feeding, but lactating women may require dosage adjustment; caution advised
Hypoglycaemia; hypokalemia, oedema; pruritus; pulpitation, nausea, rash; hypersensitivity reactions; lipoatropy or lipohypertrophy with SC Inj.
Effects may be increased by: oral antidiabetic agents, ACE inhibitors, disopyramide, fibrates, fluoxetine, MAOIs, propoxyphene, salicylates, somatostatin analog (e.g., octreotide), sulfonamide antibiotics. Effects may be decreased by: corticosteroids, niacin, danazol, diuretics, sympathomimetic agents, isoniazid, phenothiazine derivatives, somatropin, thyroid hormones, oral contraceptives, lithium. Signs of hypoglycaemia may be masked by beta-blockers, clonidine.
Diabetes mellitus
Administer SC BID (ie, before breakfast and evening meal); each dose intended to cover 2 meals or a meal and snack\r\nInject SC into abdominal wall, thigh, or upper arm
Subcutaneous\r\nDiabetes Mellitus\r\nCombination rapid-onset (faster than regular insulin) and intermediate-acting insulins in fixed dose\r\nDose regimen varies among patients depending on metabolic needs; typical daily insulin requirements range between 0.5-1 unit/kg\r\nInitially, 10 units with the largest meal of the day, dose adjustments may be made on a wkly basis according to blood glucose levels. \r\nDose should not be increased if there is hypoglycaemic episode (<70 mg/dl) during a 3-day period.
Safety and efficacy not established
Renal impairment: Dose adjustments may be required.
Hypoglycaemia. Hypersensitivity to any of the components.
Insulin lispro is a short-acting biosynthetic human insulin analogue. Insulin lispro protamine is an intermediate-acting glucose-lowering agent; it is a suspension of crystals produced from combining insulin lispro and protamine sulfate under appropriate conditions for crystal formation. They are used together for the regulation of glucose metabolism.
Renal or hepatic impairment; pregnancy, lactation; transferring from other insulin. Monitor serum glucose, potassium, electrolytes, HbA1c and lipid profile. Concomitant illness esp infections.\r\n\r\nLactation: Unknown whether distributed in breast milk; compatible with breast feeding, but lactating women may require dosage adjustment; caution advised
Hypoglycaemia; hypokalemia, oedema; pruritus; pulpitation, nausea, rash; hypersensitivity reactions; lipoatropy or lipohypertrophy with SC Inj.
Effects may be increased by: oral antidiabetic agents, ACE inhibitors, disopyramide, fibrates, fluoxetine, MAOIs, propoxyphene, salicylates, somatostatin analog (e.g., octreotide), sulfonamide antibiotics. Effects may be decreased by: corticosteroids, niacin, danazol, diuretics, sympathomimetic agents, isoniazid, phenothiazine derivatives, somatropin, thyroid hormones, oral contraceptives, lithium. Signs of hypoglycaemia may be masked by beta-blockers, clonidine.
N/A